
Pick a classification on the left and it opens on the right. Turn on Test me to hide each answer until you tap Show answer, or press Random for a quick quiz. Each entry links to the page it comes from.
Gustilo-Anderson (open fractures)
| Classification | Description | |
|---|---|---|
| Type I | An open fracture with a wound which is a. < 1cm b. clean. Infection rate: 0-2% |  |
| Type II | An open fracture with a wound which is a. > 1cm long b. not associated with extensive soft tissue damage, avulsions or flaps. Infection rate: 2-7% |  |
| Type IIIa | An open fracture where there is adequate soft tissue coverage of bone in spite of a. extensive soft tissue lacerations or flaps, or b. high energy trauma irrespective of wound size. Infection rate: 7% |  |
| Type IIIb | An open fracture with extensive soft tissue loss, with periosteal stripping and exposure of bone. Massive contamination is usual. Will require flap or graft for closure. Infection rate: 10-50% |  |
| Type IIIc | An open fracture of any size wound associated with arterial injury. Will require vascular repair. Infection rate: 25-50% | 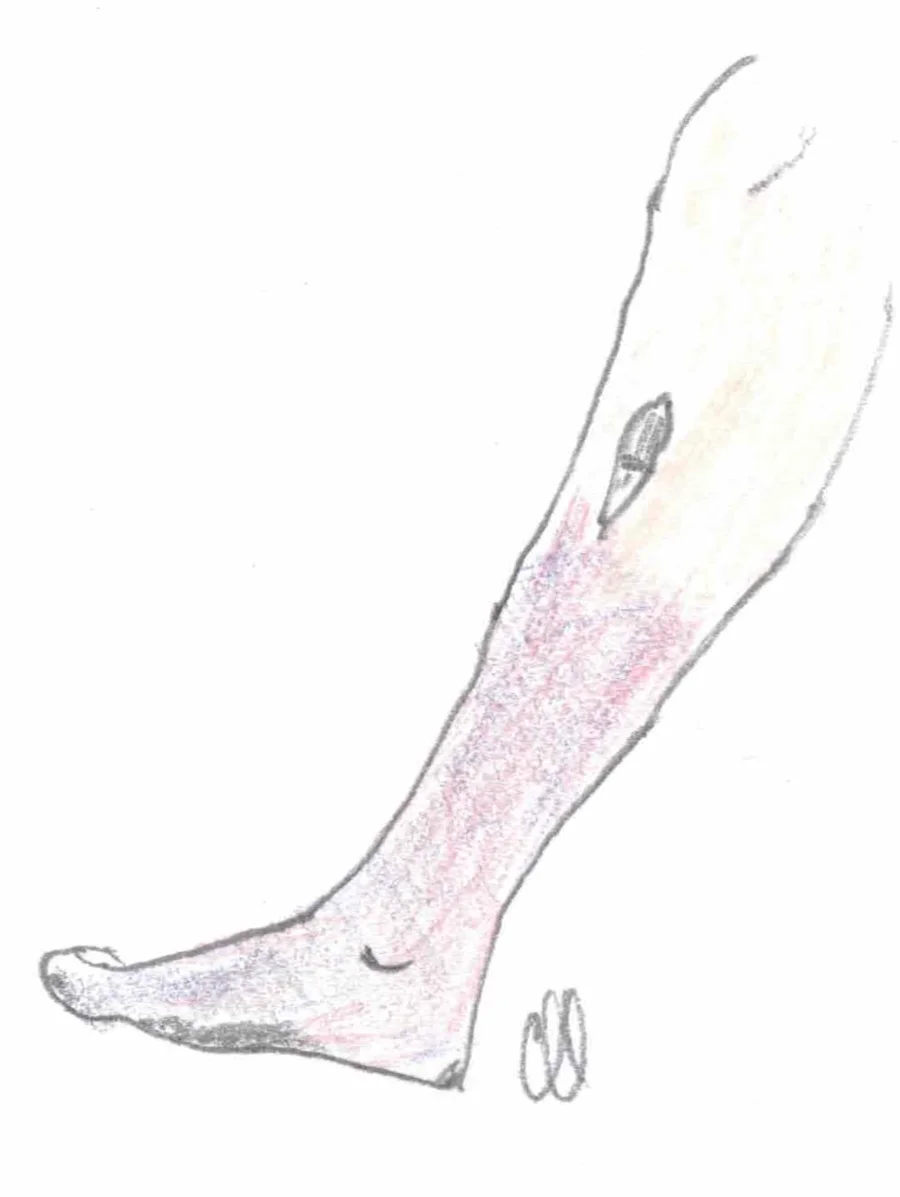 |
Tscherne (closed soft tissue injury)
| Grade | Description |
|---|---|
| 0 | little or no soft-tissue injury |
| 1 | superficial abrasion with local contusional damage to skin or muscle |
| 2 | deep contaminated abrasion with local contusional damage to skin and muscle |
| 3 | extensive contusion or crushing of skin or destruction of muscle |
Mangled Extremity Severity Score
| Component | Finding | Points |
|---|---|---|
| Vascularity | Poor pulse | 1 |
| Pulseless & poor capillary refill | 2 | |
| Totally avascular | 3 | |
| Double this score if ischaemia >6 hours | ||
| Injury (skeletal / soft tissue) | Low energy | 1 |
| Medium energy | 2 | |
| High energy | 3 | |
| Very high energy | 4 | |
| Shock | Systolic BP > 90mmHg | 0 |
| Hypotensive transiently | 1 | |
| Persistent hypotension | 2 | |
| Age | < 30 years | 0 |
| 30-50 years | 1 | |
| > 50 years | 2 |
Original publication Johansen K, Daines M, Howey T, Helfet D, Hansen St Jr. Objective criteria accurately predict amputation following lower extremity trauma. J Trauma. 1990;30(5):568-72; discussion 572-3.
| Score | Severity |
|---|---|
| 0 | No injury |
| 1 | Minor |
| 2 | Moderate |
| 3 | Serious |
| 4 | Severe |
| 5 | Critical |
| 6 | Unsurvivable |
Original publication Baker SP, O’Neill B, Haddon W Jr, Long WB. The injury severity score: a method for describing patients with multiple injuries and evaluating emergency care. J Trauma. 1974;14(3):187-96.
Abbreviated Injury Scale
| Head | 6 | Crush of Head or Brain |
|---|---|---|
| 5 | Brain Stem contusion | |
| 4 | Epidural haematoma (small) | |
| Face | 2 | Optic nerve laceration |
| 3 | External carotid laceration (major) | |
| 3 | Le Fort III fracture | |
| Neck | 5 | Crushed larynx |
| 3 | Pharynx haematoma | |
| 1 | Thyroid gland contusion | |
| Thorax | 4 | Open chest wound |
| 4 | Aorta, intima tear | |
| 2 | Oesophageal contusion | |
| 3 | Myocardial contusion | |
| 4 | Pulmonary contusion (bilateral) | |
| 2 | Two or three rib fractures | |
| Abdomen and Pelvic Contents | 4 | Bladder perforation |
| 4 | Colon transection | |
| 3 | Liver laceration >20% blood loss | |
| 3 | Retroperitoneal haematoma | |
| 4 | Splenic laceration – major | |
| Spine | 2 | Incomplete brachial plexus |
| 5 | Complete spinal cord c4 or below | |
| 3 | Herniated disc with radiculopathy | |
| 3 | Vertebral body compress >20% | |
| Upper Extremity | 3 | Amputation |
| 3 | Elbow crush | |
| 2 | Shoulder dislocation | |
| 3 | Open forearm fracture | |
| Lower Extremity | 3 | Amputation – below knee |
| 4 | Amputation – above knee | |
| 2 | Hip dislocation | |
| 2 | Knee dislocation | |
| 3 | Femoral shaft fracture | |
| 3 | Open pelvic fracture | |
| External | 3 | Hypothermia 31-30°C |
| 3 | Electrical injury with myonecrosis | |
| 3 | Second degree to third degree burns – 20-29% body surface area |
Blast and projectile injuries
| Blast type | Mechanism | Injuries |
|---|---|---|
| Primary | Overpressure wave | Tympanic membrane, lung and bowel injury |
| Secondary | Fragments and debris | Penetrating wounds and contamination |
| Tertiary | Body thrown or crushed | Fractures and traumatic amputation |
| Quaternary | Heat, smoke and toxins | Burns and inhalation injury |
Gurd criteria (fat embolism)
| Major | Minor |
|---|---|
| Respiratory insufficiency | Tachycardia and fever |
| Cerebral involvement | Retinal fat emboli and jaundice |
| Petechial rash | Anaemia, thrombocytopenia, raised ESR and fat macroglobulinaemia |
| Type | Description |
|---|---|
| Hypertrophic | A mechanical problem with good biology |
| Oligotrophic | Little callus but viable ends |
| Atrophic | A biological problem with avascular ends |
| Infected | Infected nonunion |
| Pseudarthrosis | Synovial lined cavity |
Seddon (nerve injury)
| Type | Pathology | Recovery |
|---|---|---|
| Neurapraxia | Local conduction block from segmental demyelination, axon intact, no Wallerian degeneration | Full |
| Axonotmesis | Axon and myelin disrupted with the connective tissue framework preserved, Wallerian degeneration follows | By regeneration |
| Neurotmesis | Complete disruption | None without surgery |
Sunderland (nerve injury)
| Grade | Injury | Recovery |
|---|---|---|
| I | Neurapraxia, conduction block | Full |
| II | Axon disrupted, endoneurium intact | Full, at the rate of regeneration |
| III | Endoneurium disrupted, perineurium intact | Incomplete, from axonal misdirection |
| IV | Only epineurium intact | Neuroma in continuity needing resection and repair or grafting |
| V | Complete transection | None without repair |
| VI (Mackinnon) | Mixed injury with different grades in different fascicles | Variable |
Original publication Sunderland S. A classification of peripheral nerve injuries producing loss of function. Brain. 1951;74(4):491-516.
Brooker (heterotopic ossification)
| Grade | Description |
|---|---|
| 1 | Isolated islands of bone |
| 2 | Bone spurs from femur / ilium, >1cm gap |
| 3 | Bone spurs, <1cm gap |
| 4 | Bone spurs with apparent bony ankylosis |
Original publication Brooker AF, Bowerman JW, Robinson RA, Riley Lh Jr. Ectopic ossification following total hip replacement. Incidence and a method of classification. J Bone Joint Surg Am. 1973;55(8):1629-32.
Neer (proximal humerus fractures)
| Parts | Description |
|---|---|
| 1 part | Minimally displaced, effectively all one |
| 2 part | 2 separate parts, being typically head / GT / LT and shaft. Other combinations may include an isolated GT or LT fracture |
| 3 part | 3 separate fragments. The head and LT or GT are still in continuity, otherwise all fragments are separate. |
| 4 part | GT, LT, shaft, neck all separate fragments. |
Original publication Neer Cs 2nd. Displaced proximal humeral fractures. I. Classification and evaluation. J Bone Joint Surg Am. 1970;52(6):1077-89.
Robinson (clavicle fractures)
| Subgroup | Description |
|---|---|
| 1A1 | Medial third, extra-articular, undisplaced |
| 1B1 | Medial third, extra-articular, displaced |
| 1A2 | Medial third, intra-articular, undisplaced |
| 1B2 | Medial third, intra-articular, displaced |
| 2A1 | Middle third, simple, undisplaced |
| 2A2 | Middle third, simple, displaced |
| 2B1 | Middle third, butterfly fragment |
| 2B2 | Middle third, comminuted |
| 3A1 | Lateral third (lateral to the trapezoid ligament), extra-articular, undisplaced |
| 3B1 | Lateral third, extra-articular, displaced |
| 3A2 | Lateral third, intra-articular, undisplaced |
| 3B2 | Lateral third, intra-articular, displaced |
Original publication Robinson CM. Fractures of the clavicle in the adult. Epidemiology and classification. J Bone Joint Surg Br. 1998;80(3):476-84.
Neer (lateral clavicle fractures)
| Type | Description |
|---|---|
| I | Lateral to the coracoclavicular ligaments, minimal displacement |
| IIA | Medial to the conoid ligament, both coracoclavicular ligaments attached to the distal fragment |
| IIB | Between the conoid and trapezoid ligaments, conoid torn |
| III | Extends into the acromioclavicular joint |
Original publication Neer Cs 2nd. Fractures of the distal third of the clavicle. Clin Orthop Relat Res. 1968;58:43-50.
Rockwood (acromioclavicular dislocation)
| Type | Description | Ligament injury |
|---|---|---|
| I | ACJ sprain | Incomplete AC ligament injury |
| II | ACJ disrupted, CCL intact or sprained | Complete AC, incomplete CC |
| III | Rupture of ACJ and CCL (25 to 100% subluxation) | Complete AC, complete CC |
| IV | Into trapezius | Complete AC, complete CC |
| V | High dislocation, more than 1 x clavicle width (100 to 300% subluxation). Disrupted trapezius and deltoid, end of clavicle subcutaneous | Complete AC, complete CC |
| VI | Subcoracoid dislocation | Complete AC, complete CC |
Original publication Allman Fl Jr. Fractures and ligamentous injuries of the clavicle and its articulation. J Bone Joint Surg Am. 1967;49(4):774-84.
Sternoclavicular dislocation
| Basis | Types |
|---|---|
| Direction | Anterior, more common by far Posterior, more serious injury, least common, can present with venous engorgement, SOB, difficulty swallowing secondary to obstruction of mediastinum |
| Mechanism | Traumatic, atraumatic |
| Degree | Dislocation, subluxation |
Shoulder dislocation by direction
| Type | Notes |
|---|---|
| Subcoracoid | Most common |
| Subglenoid | |
| Intrathoracic |
Glenohumeral instability
| Basis | Types |
|---|---|
| Mechanism | Traumatic, atraumatic, laxity, overuse |
| Direction | Unidirectional, anterior (98%), posterior (2%), inferior (luxatio erecta) Multidirectional, anterior/inferior, posterior/inferior, anterior/posterior/inferior |
| Chronology | Congenital, acute, chronic, locked, recurrent |
| Volition | Involuntary, voluntary |
| Degree | Subluxation, dislocation |
Posterior glenohumeral instability
| Basis | Groups |
|---|---|
| Direction | Unidirectional, posterior (smallest group) Bidirectional, posterior & inferior Multidirectional |
| Cause | Traumatic Atraumatic Acquired (baseball pitching & swimming strokes) |
| Volition | Voluntary Involuntary |
Stanmore (shoulder instability)
| Type | Description |
|---|---|
| 1 | Traumatic structural |
| 2 | Atraumatic structural |
| 3 | Muscle patterning, non-structural |
Snyder and Maffet (SLAP lesions)
| Type | Description | Frequency |
|---|---|---|
| 1 Frayed | Fraying & degeneration of superior labrum. No detachment of labrum or biceps | 11% |
| 2 Detached | Superior labrum & attached biceps tendon stripped off glenoid. Differentiate from normal anatomy, as articular cartilage of glenoid normally extends to the attachment of labrum | 41% |
| 3 Bucket handle tear of superior labrum | Displacement of central rim of labrum into joint. Peripheral labrum & biceps tendon attached to glenoid | 33% |
| 4 Bucket handle involving biceps | Bucket handle tear of superior labrum with extension into biceps tendon, which remains attached but with partial tear |
Original publication Snyder SJ, Karzel RP, Del Pizzo W, Ferkel RD, Friedman MJ. SLAP lesions of the shoulder. Arthroscopy. 1990;6(4):274-9.
| Type | Description | Treatment |
|---|---|---|
| 5 Labral tear + SLAP (extension of type 2 further down labrum) | Anteroinferior Bankart lesion extending superiorly to separate the biceps anchor | Bankart repair extended superiorly to repair the biceps anchor |
| 6 Superior flap tear (like parrot-beak tear of meniscus) | Unstable anterior or posterior flap of superior labrum with biceps anchor separation | Flap debridement and repair of the biceps anchor |
| 7 Capsular tear + SLAP | Biceps anchor separation extending anteriorly beneath the MGHL | Superior labral repair and repair of the MGHL |
Neer (impingement stages)
| Stage | Description | Age |
|---|---|---|
| I | Reversible. Oedema & haemorrhage | < 25 years |
| II | Irreversible change. Fibrosis & tendonitis IIA no tear IIB partial thickness tears | 25-40 years |
| III | Chronic. Partial & full thickness tears | > 40 years |
Original publication Neer Cs 2nd. Anterior acromioplasty for the chronic impingement syndrome in the shoulder: a preliminary report. J Bone Joint Surg Am. 1972;54(1):41-50.
Neer (rotator cuff tears)
| Group | Description |
|---|---|
| 1 | Traumatic tears. < 5% of 340 cases. < 40 years of age and result of microtrauma from overhead sports |
| 2 | Tears with dislocations. Anterior dislocation, > 40 years and in rotator interval. Multidirectional instability. Cleft tear of rotator interval. Extreme violence at any age with large cuff tear, maybe associated nerve injury |
| 3 | Impingement tears. > 40 years. 50% no history of injury |
Uhthoff (calcific tendinopathy)
| Stage | Description |
|---|---|
| Pre-Calcific stage | Fibrocartilaginous Metaplasia |
| Calcific Stage | ~No pain or chronic pain ~”Chalk” appearance ~Well-defined calcification on XR |
| Formative Stage | |
| Resting Phase | No pain or chronic pain |
| Resorptive Stage | ~Acute pain ~”Toothpaste & quot ~Fluffy appearance on XR ~Macrophage resorption |
| Post-Calcific Stage | Area heals to scar |
Frozen shoulder stages
| Phase | Features | Duration |
|---|---|---|
| Freezing | Gradual diffuse onset shoulder pain, lateral to arm at deltoid insertion. Worse at night & lying on that side. If reduce movement the pain reduced | Variable, 2-9 months |
| Frozen | Slowly progressive loss of shoulder movement with gradual subsidence of pain. Affects ADLs usually. Usually characteristic loss of ER & abduction. 10% have negligible glenohumeral movement | 4-12 months |
| Thawing | Gradually regain shoulder movement. Slow ↑ in movement with loss of discomfort | 6-9 months to regain functional ROM |
Walch (glenoid morphology)
| Type | Description |
|---|---|
| A1 | Central minor erosion, centred head |
| A2 | Central major erosion, centred head |
| B1 | Posterior narrowing and subluxation without bony erosion |
| B2 | Biconcave glenoid with posterior erosion |
| B3 | Monoconcave posterior erosion with retroversion and posterior subluxation |
| C | Excessive dysplastic retroversion |
| D | Glenoid anteversion or anterior subluxation |
Original publication Walch G, Badet R, Boulahia A, Khoury A. Morphologic study of the glenoid in primary glenohumeral osteoarthritis. J Arthroplasty. 1999;14(6):756-60.
Mason (radial head fractures)
| Type | Description | Management |
|---|---|---|
| 1 | Undisplaced / <2mm displacement, and no mechanical block | Conservative management with immobilisation in backslab / sling followed by early mobilisation from ~2/52 onwards |
| 2 | Comminution / displacement, involving up to 50%, possible mechanical block | ORIF. Can consider fragment excision, but only if <25% of radial head and at risk of causing instability |
| 3 | Comminuted fracture involving the whole head, with mechanical block present | Consider ORIF, or radial head replacement |
| 4 | Radial head and ulna-humeral dislocation |
Original publication Mason ML. Some observations on fractures of the head of the radius with a review of one hundred cases. Br J Surg. 1954;42(172):123-32.
Regan and Morrey (coronoid fractures)
| Type | Description |
|---|---|
| I | Tip of process |
| II | < 50% of process |
| III | > 50% of process |
Original publication Regan W, Morrey B. Fractures of the coronoid process of the ulna. J Bone Joint Surg Am. 1989;71(9):1348-54.
AO (olecranon fractures)
| Type | Description |
|---|---|
| 21-A | Extra-articular |
| 21-B | Articular, involving the surface of one bone |
| 21-C | Articular, involving the surface of both bones |
Original publication Meinberg EG, Agel J, Roberts CS, Karam MD, Kellam JF. Fracture and Dislocation Classification Compendium-2018. J Orthop Trauma. 2018;32 Suppl 1:S1-S170.
Elbow dislocation
| Basis | Types |
|---|---|
| Simple or complex | Complex dislocations are associated with fractures |
| Final position of ulna | Posterior, posterior-lateral |
| Degree | Complete, disrupted medial collateral ligament Perched, <10% pts, disrupted lateral collateral ligament ± medial collateral ligament |
| Associated fractures | 25-50% |
Complex elbow instability
| Type | Description |
|---|---|
| Simple dislocation | Without associated fracture |
| Complex dislocation | With associated fracture |
Mayo (rheumatoid elbow)
| Grade | Description |
|---|---|
| I | Synovitis with normal radiographs |
| II | Joint space narrowing with preserved architecture |
| III | Altered architecture |
| IV | Gross destruction |
Bado (Monteggia fractures)
| Type | Description |
|---|---|
| 1 | Fracture of proximal or middle third of ulna, with anterior dislocation of radial head. Most common fracture pattern (~60%). Posterior angulation of distal ulna fragment. |
| 2 | Fracture of proximal or middle third of ulna, with posterior dislocation of the radial head. Anterior angulation of distal ulna fragment. |
| 3 | Fracture of ulna with lateral dislocation of radial head. More common in paediatric patients |
| 4 | Anterior dislocation of radial head with radial shaft fracture. |
Original publication Bado JL. The Monteggia lesion. Clin Orthop Relat Res. 1967;50:71-86.
Galeazzi fractures
| System | Type 1 | Type 2 |
|---|---|---|
| Location of distal radius compared to ulna | Volar displacement | Dorsal displacement |
| Rettig and Raskin, location of fracture | <7.5cm from articular surface. Associated with >50% DRUJ injury | >7.5cm from articular surface. Associated with <5% DRUJ instability |
Original publication Rettig ME, Raskin KB. Galeazzi fracture-dislocation: a new treatment-oriented classification. J Hand Surg Am. 2001;26(2):228-35.
Minami (capitellar OCD)
| Grade | Description |
|---|---|
| I | Translucent shadow in mid capitellum |
| II | Clear zone between lesion and adjacent bone |
| III | Loose body |
Frykman (distal radius)
| Fracture | No Distal Ulna Fracture | With Distal Ulnar Fracture |
|---|---|---|
| Extra-articular | I | II |
| Intra-articular | ||
| Radiocarpal Joint | III | IV |
| Radioulnar Joint | V | VI |
| RC + RU Joint | VII | VIII |
Universal (distal radius)
| Type | Description |
|---|---|
| I | Nonarticular, nondisplaced |
| II | Nonarticular, displaced . A. Reducible, stable . B. Reducible, unstable . C. Irreducible |
| III | Articular, nondisplaced |
| IV | Articular, displaced . A. Reducible, stable . B. Reducible, unstable . C. Irreducible . D. Complex (shear, joint depression, fracture/ dislocation) |
Cooney (distal radius)
| Type | Description |
|---|---|
| I | Intra-articular & undisplaced |
| II | Displaced involving the radioscaphoid joint |
| III | Displaced involving the radiolunate joint |
| IV | Displaced involving radioscaphoid, radiolunate & sigmoid notch |
Melone (distal radius)
| Type | Description |
|---|---|
| Type I | Undisplaced minimal comminution |
| Type II | Lunate Fossa die punch . Anterior displacement . Posterior displacement |
| Type III | Radial shaft component & above |
| Type IV | Transverse split with rotation of artic fragments |
Fernandez (distal radius)
| Type | ||
|---|---|---|
| 1 | Bending | metaphysis fails due to tensile stress (Colles & Smith fractures) |
| 2 | Compression | die punch fractures |
| 3 | Shearing | fractures of the joint surface such as Barton fractures & fracture of the radial styloid process |
| 4 | Avulsion | fracture of ligamentous attachments (fracture of the ulnar & radial styloid processes) |
| 5 | Combination | Combinations of types one through four & high velocity injuries |
Palmer (TFCC tears)
| Class | Description |
|---|---|
| 1 | Traumatic |
| 2 | Degenerative |
Original publication Palmer AK. Triangular fibrocartilage complex lesions: a classification. J Hand Surg Am. 1989;14(4):594-606.
Geissler (wrist arthroscopy)
| Grade | Description | Treatment |
|---|---|---|
| I | Attenuation or haemorrhage within ligament. No step | Cast immobilisation |
| II | Incongruency or step-off in midcarpal space | Arthroscopic pinning. Use K wire as joystick to reduce |
| III | Step-off on both sides. Probe may be passed between bones | Arthroscopic or open repair |
| IV | Gross instability | Open repair |
Gedda (thumb base fractures)
| Type | Description |
|---|---|
| 1 | Large single ulnar fragment with subluxation of MC base |
| 2 | Impaction fracture without subluxation of MC base |
| 3 | Small ulnar avulsion fragment with CMC dislocation |
Eaton and Littler (thumb CMC arthritis)
| Stage | Radiographic features |
|---|---|
| I | Normal or widened joint |
| II | Osteophytes under 2 mm |
| III | Osteophytes 2 mm or more and sclerosis |
| IV | Scaphotrapeziotrapezoid (STT) involvement |
Original publication Eaton RG, Littler JW. Ligament reconstruction for the painful thumb carpometacarpal joint. J Bone Joint Surg Am. 1973;55(8):1655-66.
SLAC wrist (Watson)
| Stage | Arthritis |
|---|---|
| I | Radial styloid and scaphoid |
| II | Entire radioscaphoid joint |
| III | Capitolunate joint |
| IV | Pancarpal arthritis including the radiolunate joint |
Original publication Watson HK, Ballet FL. The SLAC wrist: scapholunate advanced collapse pattern of degenerative arthritis. J Hand Surg Am. 1984;9(3):358-65.
SNAC wrist
| Stage | Arthritis |
|---|---|
| I | Radial styloid and distal scaphoid fragment |
| II | Scaphocapitate joint |
| III | Capitolunate joint, with the proximal pole articulation usually preserved |
Original publication Vender MI, Watson HK, Wiener BD, Black DM. Degenerative change in symptomatic scaphoid nonunion. J Hand Surg Am. 1987;12(4):514-9.
Lichtman (Kienbock disease)
| Stage | Findings |
|---|---|
| 1 Normal | No radiographic changes. May be possible to see on MRI |
| 2 Sclerosis | Density changes. Sclerosis of proximal pole |
| 3A Fragmentation | May be evidence of compression fracture. Radiolucent or radiodense line |
| 3B Collapse | Collapse of lunate. Flattening |
| 4 Degeneration | Pancarpal arthritis |
Original publication Lichtman DM, Mack GR, MacDonald RI, Gunther SF, Wilson JN. Kienböck’s disease: the role of silicone replacement arthroplasty. J Bone Joint Surg Am. 1977;59(7):899-908.
Carpal instability types
| Type | Description |
|---|---|
| DISI | Dorsi-flexion (Dorsal Intercalated Segment Instability). Most common, where lunate is rotated into dorsi-flexion (zig zag alignment of radiolunatocapitate alignment) |
| VISI | Palmar flexion (Volar Intercalated Segment Instability) |
| Ulnar translocation | Abnormal translocation of lunate ulnarward Type 1 entire carpus is translocated ulnarward Type 2 relationship between radius & scaphoid is normal but scapholunate gap is wide Rheumatoid |
| Dorsal subluxation | Malunion fracture distal radius with reversal of normal palmar tilt |
Original publication Linscheid RL, Dobyns JH, Beabout JW, Bryan RS. Traumatic instability of the wrist. Diagnosis, classification, and pathomechanics. J Bone Joint Surg Am. 1972;54(8):1612-32.
Tubiana (Dupuytren disease)
| Stage | Total flexion deformity |
|---|---|
| N | Nodule without contracture |
| 1 | 0 to 45 degrees |
| 2 | 45 to 90 degrees |
| 3 | 90 to 135 degrees |
| 4 | Over 135 degrees |
Original publication Tubiana R. Evaluation of deformities in Dupuytren’s disease. Ann Chir Main. 1986;5(1):5-11.
Bayne and Klug (radial longitudinal deficiency)
| Type | Description |
|---|---|
| 0 | Normal radius with carpal or thumb anomaly |
| 1 | Short distal radius |
| 2 | Hypoplastic radius |
| 3 | Partial absence |
| 4 | Complete absence, the commonest |
Original publication Bayne LG, Klug MS. Long-term review of the surgical treatment of radial deficiencies. J Hand Surg Am. 1987;12(2):169-79.
AO Spine (thoracolumbar)
| Type | Description |
|---|---|
| A | Compression. A3 incomplete burst of one endplate, A4 complete burst of both |
| B | Tension band failure. B1 bony Chance, B3 anterior hyperextension injury |
| C | Displacement or translation |
| Total score | Management |
|---|---|
| 3 or less | Non-operative |
| 4 | Indeterminate |
| 5 or more | Surgery |
Denis (sacral zones)
| Zone | Description |
|---|---|
| I | Lateral to the foramina, occasional L5 root injury |
| II | Through the foramina, sacral root injury |
| III | Medial into the canal, highest rate of bowel, bladder and sexual dysfunction |
Original publication Denis F, Davis S, Comfort T. Sacral fractures: an important problem. Retrospective analysis of 236 cases. Clin Orthop Relat Res. 1988;227:67-81.
Levine and Edwards (C2 spondylolisthesis)
| Type | Description |
|---|---|
| I | Under 3 mm displacement, no angulation |
| II | Displacement and angulation |
| IIa | Angulation without translation, distraction makes it worse |
| III | With facet dislocation |
Original publication Levine AM, Edwards CC. The management of traumatic spondylolisthesis of the axis. J Bone Joint Surg Am. 1985;67(2):217-26.
Fielding and Hawkins (atlantoaxial rotatory)
| Type | Description |
|---|---|
| I | Rotatory fixation, no anterior displacement, ligament intact, most common |
| II | Anterior displacement 3 to 5 mm, one lateral mass acting as pivot |
| III | Anterior displacement more than 5 mm |
| IV | Posterior displacement |
Original publication Fielding JW, Hawkins RJ. Atlanto-axial rotatory fixation. (Fixed rotatory subluxation of the atlanto-axial joint). J Bone Joint Surg Am. 1977;59(1):37-44.
Ranawat (rheumatoid neurology)
| Class | Description |
|---|---|
| 1 | Pain, no neurological deficit |
| 2 | Subjective weakness, dysaesthesia and hyperreflexia |
| 3A | Objective weakness and long tract signs, ambulatory |
| 3B | Objective weakness and long tract signs, non-ambulatory |
Original publication Ranawat CS, O’Leary P, Pellicci P, Tsairis P, Marchisello P, Dorr L. Cervical spine fusion in rheumatoid arthritis. J Bone Joint Surg Am. 1979;61(7):1003-10.
mJOA (cervical myelopathy)
| Severity | mJOA score |
|---|---|
| Mild | 15 to 17 |
| Moderate | 12 to 14 |
| Severe | Under 12 |
Quebec (whiplash)
| Group | Description |
|---|---|
| 1 | ~ symptoms related to their injuries ~ no abnormality on physical examination. |
| 2 | ~ symptoms ~ reduced range of movement of the cervical spine but no abnormal neurological signs. |
| 3 | ~ symptoms ~ reduced range of cervical movement ~ evidence of objective neurological loss. |
Modic (endplate changes)
| Type | T1 | T2 | Notes |
|---|---|---|---|
| I | Decreased signal | Increased signal | Found in 4% of cases. Must be distinguished from disc space infection (in disc space infection discs have ↑ signal intensity on T2 weighted images, & in degeneration discs have ↓ T2 signal intensity) |
| II | Increased signal | Isointense or slightly ↑ | Found in 16% of cases. Represents fatty marrow conversion |
| III | Low signal | Low signal | Bony sclerosis seen on plain films |
Original publication Modic MT, Steinberg PM, Ross JS, Masaryk TJ, Carter JR. Degenerative disk disease: assessment of changes in vertebral body marrow with MR imaging. Radiology. 1988;166(1 Pt 1):193-9.
Schizas (lumbar stenosis)
| Grade | Description |
|---|---|
| A | CSF clearly visible |
| B | Rootlets fill the sac but can be individualised |
| C | No CSF, rootlets indistinguishable, posterior fat present |
| D | No CSF and no posterior epidural fat |
Disc herniation by position
| Position | Notes |
|---|---|
| Central | Can affect traversing nerve roots bilaterally, & cauda equina if large enough |
| Posterolateral | Commonest site. Herniation is to one side of PLL. Impingement of nerve root of lower vertebra |
| Foraminal | Impingement of exiting nerve root (vertebra above), 10% |
| Extraforaminal or far lateral |
Wiltse (spondylolisthesis)
| Type | Description |
|---|---|
| I | Dysplastic, congenital deficiency of L5 to S1 facets with intact pars |
| II | Isthmic, pars lesion from stress fracture or elongation |
| III to VI | Degenerative, traumatic, pathological and iatrogenic, mostly adult |
Original publication Wiltse LL, Newman PH, Macnab I. Classification of spondylolisis and spondylolisthesis. Clin Orthop Relat Res. 1976(117):23-9.
Meyerding (slip grade)
| Grade | Slip |
|---|---|
| 1 | 1 to 25% |
| 2 | 26 to 50% |
| 3 | 51 to 75% |
| 4 | 76 to 100% |
| 5 | More than 100%, spondyloptosis |
Key reference (original not indexed in PubMed) Koslosky E, Gendelberg D. Classification in Brief: The Meyerding Classification System of Spondylolisthesis. Clin Orthop Relat Res. 2020;478(5):1125-1130.
Resnick criteria (DISH)
| Criterion | |
|---|---|
| 1 | Flowing ossification along the anterolateral aspect of at least four contiguous vertebral bodies |
| 2 | Relative preservation of disc height |
| 3 | No facet ankylosis and no sacroiliac erosion, sclerosis or fusion |
Original publication Resnick D, Niwayama G. Radiographic and pathologic features of spinal involvement in diffuse idiopathic skeletal hyperostosis (DISH). Radiology. 1976;119(3):559-68.
Os odontoideum
| Type | Description |
|---|---|
| Orthotopic | Ossicle moves with the anterior arch of C1 |
| Dystopic | Ossicle fused to the clivus or displaced |
Basilar invagination
| Type | Causes |
|---|---|
| Primary (congenital) | Associated with vertebral anomalies (atlanto-occipital fusion, hypoplasia of the atlas, Klippel-Feil) Associated with skeletal dysplasias (achondroplasia, spondyloepiphyseal dysplasia, Morquio syndrome) |
| Secondary | Skull softening disorders (severe osteoporosis, osteomalacia, rickets, Paget’s, osteogenesis imperfecta, RA, neurofibromatosis) |
Cervical rib
| Type | Description |
|---|---|
| True neurogenic | Objective neurological deficit |
| Disputed neurogenic | Symptoms and no objective findings |
| Arterial | |
| Venous |
Tile (pelvic ring)
| Type | Description | Subtypes |
|---|---|---|
| A | Stable pelvic ring injury | A1 avulsion of ilium A2 stable iliac wing fracture or stable minimally displaced ring fractures A3 transverse fractures of sacrum & coccyx |
| B | Partially stable, rotationally unstable, vertically stable | B1 open book (external rotation with disrupted pubic symphysis). Stage 1 < 2.5cm, no posterior injury. Stage 2 >2.5cm, SS & ST ligaments disrupted. Stage 3 as above, bilateral B2 lateral compression, ipsilateral anterior & posterior fracture B3 lateral compression, contralateral anterior & posterior fracture (bucket-handle) |
| C | Unstable, disruption of SIJ/ SS & ST ligs/ pelvic floor | C1 unilateral C2 bilateral C3 associated with acetabular fracture |
Original publication Tile M. Pelvic ring fractures: should they be fixed? J Bone Joint Surg Br. 1988;70(1):1-12.
Letournel (acetabular fractures)
| Type | Notes |
|---|---|
| Posterior wall | Commonest type (25-33%). Very commonly associated with a hip dislocation (eg 86/100 in Moed’s study) |
| Posterior column | |
| Anterior wall | |
| Anterior column | |
| Transverse | Transtectal – transverse fracture line crosses superior acetabular articular surface Juxtatectal – fracture line crosses at the junction of the superior acetabular articular surface & the superior cotyloid fossa Infratectal – fracture line crosses through the cotyloid fossa |
| Type | Notes |
|---|---|
| Associated posterior column & posterior wall | |
| Associated transverse & posterior wall | |
| T shaped | |
| Associated anterior column & posterior hemitransverse | Subtle distinction from T shaped fractures. In the T shaped fracture the fracture line is horizontal with a stem; in the anterior column/posterior hemitransverse the anterior component is higher up & typically more displaced than the posterior component |
| Both column | The essential component of this fracture is that all elements of the articular cartilage are divided from the ilium. This sets this type of fracture apart from the transverse, T shaped, associated anterior column & posterior hemitransverse & associated transverse & posterior wall fractures |
Original publication Judet R, Judet J, Letournel E. Fractures of the acetabulum: classification and surgical approaches for open reduction. preliminary report. J Bone Joint Surg Am. 1964;46:1615-46.
Garden (intracapsular hip)
| Type | Description | Management |
|---|---|---|
| 1 | Impacted / incomplete fracture | Can sometimes be managed with DHS / internal fixation. Risk of AVN significantly depends on posterior comminution due to the posterior ascending blood supply. |
| 2 | Complete fracture, undisplaced | Can be managed with DHS / internal fixation |
| 3 | Complete fracture, <50% displacement | Displaced, manage as for Garden 4 |
| 4 | >50% or completely displaced | Expect AVN, manage with primary THR or hemiarthroplasty |
Key reference (original not indexed in PubMed) Kazley JM, Banerjee S, Abousayed MM, Rosenbaum AJ. Classifications in Brief: Garden Classification of Femoral Neck Fractures. Clin Orthop Relat Res. 2018;476(2):441-445.
Pauwels (femoral neck)
| Type | Fracture angle from horizontal plane |
|---|---|
| 1 | Less than 30° |
| 2 | 30-50° |
| 3 | Greater than 50° |
Evans (intertrochanteric)
| Type | Description |
|---|---|
| I | Fracture line extends upward and outward from the lesser trochanter . Further subdivided . Stable . Unstable . Stability restored by anatomical reduction . Stability unrestored by anatomical reduction |
| II | reverse obliquity fracture, the major fracture line extends outward and downward from the lesser trochanter |
AO (trochanteric fractures)
| Group | Description |
|---|---|
| A1 | uncomminuted |
| A2 | increasing comminution |
| A3 | subtrochanteric extensions or reverse obliquity |
Seinsheimer (subtrochanteric)
| Type | Description |
|---|---|
| I | Nondisplaced fracture or one with less than 2 mm of displacement |
| II | Two-part fracture |
| IIa | Transverse fracture |
| IIb | Spiral configuration with the lesser trochanter attached to proximal fragment |
| IIc | Spiral configuration with the lesser trochanter attached to distal fragment |
| III | Three-part fracture |
| IIIa | Three-part spiral configuration with the lesser trochanter a part of the third fragment |
| IIIb | Three-part spiral configuration with the third part a butterfly fragment |
| IV | Comminuted fracture with four or more fragments |
| V | Subtrochanteric-intertrochanteric configuration |
Russell-Taylor (subtrochanteric)
| Type | Description |
|---|---|
| I | fracture does not extend into piriformis fossa |
| Ia | comminution and fracture lines extend from below lesser trochanter to femoral isthmus |
| Ib | fracture lines and comminution involve area of lesser trochanter to isthmus |
| II | fracture extends proximally into greater trochanter and involves piriformis fossa |
| IIa | no significant comminution or fracture of lesser trochanter |
| IIb | significant comminution of medial femoral cortex and loss of continuity of lesser trochanter |
Thompson and Epstein (posterior hip dislocation)
| Type | Description |
|---|---|
| I | Simple or minor posterior wall fragment |
| II | Large single posterior wall fragment |
| III | Comminuted posterior wall |
| IV | Acetabular floor fracture |
| V | Femoral head fracture |
Original publication Thompson VP, Epstein HC. Traumatic dislocation of the hip; a survey of two hundred and four cases covering a period of twenty-one years. J Bone Joint Surg Am. 1951;33-A(3):746-78; passim.
Pipkin (femoral head fractures)
| Type | Description |
|---|---|
| I | Below the fovea |
| II | Above the fovea |
| III | With femoral neck fracture |
| IV | With acetabular fracture |
Original publication Pipkin G. Treatment of grade IV fracture-dislocation of the hip. J Bone Joint Surg Am. 1957;39-A(5):1027-42 passim.
Fullerton and Snowdy (femoral neck stress)
| Type | Description |
|---|---|
| Tension | Along the superior neck |
| Compression | Along the inferomedial neck |
| Displaced |
Original publication Fullerton Lr Jr, Snowdy HA. Femoral neck stress fractures. Am J Sports Med. 1988;16(4):365-77.
Vancouver (periprosthetic THR)
| Type | Description | Management |
|---|---|---|
| A | Fractures around the GT | If less than 2cm displacement, attempt non-operative management. If >2cm displacement, unstable, or otherwise dysfunctional, ORIF |
| B1 | Fractures around the stem, stable stem | ORIF |
| B2 | Fractures around the stem, unstable stem | Revise to long stem prosthesis, and ORIF |
| C | Fractures distal to the stem | Leave THR alone, just ORIF the femoral shaft |
Original publication Duncan CP, Masri BA. Fractures of the femur after hip replacement. Instr Course Lect. 1995;44:293-304.
Crowe (adult DDH)
| Type | Subluxation |
|---|---|
| I | Under 50% |
| II | 50 to 75% |
| III | 75 to 100% |
| IV | Over 100% |
Original publication Crowe JF, Mani VJ, Ranawat CS. Total hip replacement in congenital dislocation and dysplasia of the hip. J Bone Joint Surg Am. 1979;61(1):15-23.
Hartofilakidis (adult DDH)
| Type | Description |
|---|---|
| A | Head within the true acetabulum |
| B | Low dislocation, false acetabulum overlapping the true |
| C | High dislocation, no contact with the true acetabulum |
Femoroacetabular impingement
| Type | Description |
|---|---|
| Cam | Aspherical anterosuperior head neck junction, young male athletes, after SCFE or Perthes disease |
| Pincer | Global (coxa profunda, protrusio) or focal (retroversion) overcoverage, more common in women |
| Mixed | The most common pattern |
Original publication Ganz R, Parvizi J, Beck M, Leunig M, Nötzli H, Siebenrock KA. Femoroacetabular impingement: a cause for osteoarthritis of the hip. Clin Orthop Relat Res. 2003(417):112-20.
Hip-spine classification
| Group | Sagittal alignment | Spine mobility |
|---|---|---|
| 1A | Normal alignment, PI − LL ≤10° | Normal mobility |
| 1B | Normal alignment, PI − LL ≤10° | Stiff spine |
| 2A | Flatback deformity, PI − LL >10° | Normal mobility |
| 2B | Flatback deformity, PI − LL >10° | Stiff spine. Highest risk, malaligned spine that cannot compensate |
Ficat and Arlet (femoral head AVN)
| Stage | Clinical | Imaging |
|---|---|---|
| 0 | Preclinical | Radiographs normal, bone scan cold, MRI double line on T2 |
| I | Onset of ischaemia | Radiographs normal, changes on MRI or bone scan only |
| II | Pain | Early cystic and sclerotic change with a preserved head contour |
| III | Structural change | Crescent sign and flattening of the head |
| IV | Degenerative change | Joint space narrowing and secondary osteoarthritis |
Original publication Ficat RP. Idiopathic bone necrosis of the femoral head. Early diagnosis and treatment. J Bone Joint Surg Br. 1985;67(1):3-9.
ARCO (femoral head AVN)
| Stage | Description |
|---|---|
| 0 | Bone biopsy = AVN All other Ix normal |
| 1 | Normal X-ray MRI +ve |
| 2 | Typical X-ray changes no collapse |
| 3 | Collapse For stage 3 collapse on XR subdivided A = 2mm or < 15% B = 2-4mm or 15-30% C = > 4mm or > 30% |
| 4 | Osteoarthritis |
Kellgren and Lawrence (osteoarthritis)
| Grade | Description |
|---|---|
| 0 | None |
| 1 | Doubtful |
| 2 | Minimal |
| 3 | Moderate |
| 4 | Severe |
Original publication Kellgren JH, Lawrence JS. Radiological assessment of osteo-arthrosis. Ann Rheum Dis. 1957;16(4):494-502.
AO/OTA 33 (distal femur)
| Type | Description |
|---|---|
| A | Extra-articular |
| B | Partial articular |
| C | Complete articular |
Original publication Meinberg EG, Agel J, Roberts CS, Karam MD, Kellam JF. Fracture and Dislocation Classification Compendium-2018. J Orthop Trauma. 2018;32 Suppl 1:S1-S170.
Su (periprosthetic distal femur)
| Type | Description |
|---|---|
| I | Proximal to the femoral component |
| II | Originating at the proximal end of the component |
| III | Any part distal to the upper edge of the anterior flange |
Original publication Su ET, DeWal H, Di Cesare PE. Periprosthetic femoral fractures above total knee replacements. J Am Acad Orthop Surg. 2004;12(1):12-20.
Schatzker (tibial plateau)
| Type | Description | Features |
|---|---|---|
| I | Split of lateral plateau | ~seen in young people with strong bone ~Often associated with tear of lateral meniscus, which is trapped in fracture |
| II | Split depression fracture | ~Caused by valgus blow with axial loading ~Typically occurs in patients older than 40 |
| III | Pure depression (die punch) of lateral tibial plateau | ~Central depressions are usually more stable than lateral or posterior |
| IV | Fracture of medial tibial plateau | ~Much less common, associated with large forces. ~Often associated with lateral collateral ligament injuries ~Many of these injuries represent knee dislocation that has reduced ~fracture pattern most associated with vascular injury |
| V | Bicondylar fracture | ~Usually result of pure axial load applied to knee ~hallmark of this injury is that at least small part of metaphysis remains as part of joint |
| VI | Plateau fracture with complete dissociation of metaphysis from diaphysis |
Hohl and Moore (plateau fracture dislocation)
| Type | Description |
|---|---|
| I | Coronal split fracture |
| II | Entire condylar fracture |
| III | Rim Avulsion fracture |
| IV | Rim Compression fracture |
| V | Four part fracture |
Patella fractures
| Type | Description |
|---|---|
| Transverse | Most common, often from indirect quadriceps loading |
| Upper or lower pole | Extra-articular avulsions of quadriceps or patellar tendon |
| Vertical or marginal | Direct load in flexion, extensor mechanism usually intact |
| Stellate or comminuted | Direct blow, often with cartilage damage |
| Osteochondral | After patellar dislocation, medial facet or lateral femoral condyle |
| Sleeve fracture | In children, cartilage avulsed from the lower pole with a small bony fragment |
Lewis and Rorabeck (periprosthetic TKR)
| Type | Description | Management |
|---|---|---|
| 1 | Fracture above the implant, non- or minimally displaced, with no notable angulation and a stable implant | Can be managed conservatively, IMN / ORIF / MIPO |
| 2 | Fracture above the implant, with displacement and / or angulation | IMN / ORIF / MIPO |
| 3 | Fracture through level of implant, with unstable implant | Distal femur replacement |
Original publication Rorabeck CH, Taylor JW. Classification of periprosthetic fractures complicating total knee arthroplasty. Orthop Clin North Am. 1999;30(2):209-14.
Ortiguera and Berry (patella after TKA)
| Type | Description | Treatment |
|---|---|---|
| I | Stable implant, intact extensor mechanism | Non-operative |
| II | Extensor mechanism disrupted | Extensor mechanism repair with partial patellectomy or ORIF |
| IIIa | Loose patellar component, good bone stock | Component revision or resection arthroplasty |
| IIIb | Loose patellar component, poor bone stock | Component removal with patelloplasty or total patellectomy |
Original publication Ortiguera CJ, Berry DJ. Patellar fracture after total knee arthroplasty. J Bone Joint Surg Am. 2002;84(4):532-40.
Knee dislocation by direction
| Direction | Frequency |
|---|---|
| Anterior | 31% |
| Posterior | 25% |
| Lateral | 13% |
| Medial | 3% |
| Rotary | 4%, usually posterolateral |
Original publication Kennedy JC. Complete dislocation of the knee joint. J Bone Joint Surg Am. 1963;45:889-904.
Fanelli (posterolateral corner)
| Type | Description |
|---|---|
| A | External rotation only |
| B | Adds mild varus from partial FCL injury |
| C | Adds marked varus from complete FCL and capsular disruption |
Original publication Fanelli GC, Larson RV. Practical management of posterolateral instability of the knee. Arthroscopy. 2002;18(2 Suppl 1):1-8.
Hughston (posterolateral instability)
| Grade | Varus opening |
|---|---|
| I | 0 to 5 mm |
| II | 6 to 10 mm |
| III | Over 10 mm |
Original publication Hughston JC, Andrews JR, Cross MJ, Moschi A. Classification of knee ligament instabilities. Part II. The lateral compartment. J Bone Joint Surg Am. 1976;58(2):173-9.
Noyes (varus knee)
| Type | Description |
|---|---|
| Primary varus | Osseous tibiofemoral varus |
| Double varus | Adds lateral tibiofemoral separation from lateral laxity |
| Triple varus | Adds varus recurvatum from posterolateral and posterior capsular insufficiency |
Original publication Noyes FR, Barber-Westin SD, Hewett TE. High tibial osteotomy and ligament reconstruction for varus angulated anterior cruciate ligament-deficient knees. Am J Sports Med. 2000;28(3):282-96.
Watanabe (discoid meniscus)
| Type | Description | Treatment of symptomatic tears |
|---|---|---|
| 1 Complete (stable), most common | Discoid meniscus covers tibial plateau. Lateral ligaments are intact, therefore stable | Saucerization to stable peripheral rim of 6-8 mm |
| 2 Incomplete | Similar to complete, covers less of the plateau | Saucerization to stable peripheral rim of 6-8 mm |
| 3 Wrisberg ligament type (unstable) | Deficiency of posterior horn meniscal tibial ligaments. Unstable and hypermobile posterior horn. On knee extension, abnormal meniscus is pulled posteromedially into the intercondylar notch (instead of gliding forward) due to the action of the meniscofemoral ligaments. Probably responsible for the true “snapping knee” | Try to repair to reattach the posterior horn. Meniscectomy may be needed since it lacks posterior meniscal tibial attachments & has unstable posterior horn. Meniscal transplant not yet shown to be effective in skeletally immature patients |
Plica
| Type | Features |
|---|---|
| Suprapatellar | Five types (midline, medial, lateral, incomplete, complete). Complete type seals off pouch completely |
| Medial patellar | Least common. Originates from medial wall of knee joint and runs obliquely down to insert in medial infrapatellar fat pad. Most likely to be symptomatic, gets caught between patella & femur |
| Infrapatellar (ligamentum mucosum) | From notch to fat pad. Most common. Always asymptomatic |
Outerbridge (cartilage)
| Grade | Description |
|---|---|
| I | Softening |
| II | Fissuring under 1.3 cm |
| III | Fissuring over 1.3 cm |
| IV | Erosion to subchondral bone |
Original publication Outerbridge RE. The etiology of chondromalacia patellae. J Bone Joint Surg Br. 1961;43-B:752-7.
ICRS (cartilage)
| Grade | Description |
|---|---|
| 1 | Superficial |
| 2 | Under half depth |
| 3 | Over half depth |
| 4 | Through subchondral bone |
Original publication Brittberg M, Winalski CS. Evaluation of cartilage injuries and repair. J Bone Joint Surg Am. 2003;85-A Suppl 2:58-69.
SONK staging
| Stage | Description | |
|---|---|---|
| 1 | incipient stage | ~ Severe pain ~ X-ray normal or some focal osteoporosis ~ Bone scan & MRI positive |
| 2 | avascular stage | ~ Pain ~ X-ray: radiolucent oval shadow on the medial femoral condyle with some flattening of the articular surface. ~ Bone scan & MRI positive |
| 3 | collapsed stage | ~ Pain ~ X-ray: collapse of the subchondral bone plate with a calcified plate & clear sclerotic halo |
| 4 | degenerative stage | ~ Severe pain with or without deformity ~ X-ray: shallow concave articular surface with secondary OA changes, a narrowed joint space & varus deformity. |
Ruedi and Allgower (pilon)
| Grade | Description |
|---|---|
| 1 | Articular fracture without significant displacement (cleavage) |
| 2 | Articular fracture with articular incongruity |
| 3 | Comminuted compression fracture with articular incongruity |
Original publication Rüedi TP, Allgöwer M. The operative treatment of intra-articular fractures of the lower end of the tibia. Clin Orthop Relat Res. 1979(138):105-10.
Danis-Weber (ankle)
| Type | Level | Notes |
|---|---|---|
| A | Below syndesmosis | No potential for syndesmotic injury |
| B | At level of syndesmosis | Potential for syndesmotic injury. Can assess for natural trajectory and presence of any shift, assess deltoid ligaments for associated injuries |
| C | Above syndesmosis | Presumption of syndesmosis and deltoid injury. Requires stabilisation of syndesmosis |
Lauge-Hansen (ankle)
| Mechanism | Result |
|---|---|
| Supination-adduction | Weber A fracture +/- medial malleolar fracture |
| Supination-external rotation | Weber B fracture, +/- medial or posterior malleolar fracture |
| Pronation-external rotation | Weber C fracture |
| Pronation-abduction | Weber C fracture |
Original publication Lauge-Hansen N. Fractures of the ankle. II. Combined experimental-surgical and experimental-roentgenologic investigations. Arch Surg (1920). 1950;60(5):957-85.
Herscovici (medial malleolus)
| Hervscovici Classification | |
| A | Avulsion fracture of medial malleolus tip, involves deltoid ligament |
| B | Intermediate fracture |
| C | Fracture at the level of the plafond |
| D | Plafond fracture/Pilon Fracture |
Haraguchi (posterior malleolus)
| Type | Description |
|---|---|
| 1 | Posterolateral oblique |
| 2 | Medial extension |
| 3 | Small shell fragment |
Original publication Haraguchi N, Haruyama H, Toga H, Kato F. Pathoanatomy of posterior malleolar fractures of the ankle. J Bone Joint Surg Am. 2006;88(5):1085-92.
Syndesmosis injury (ESSKA)
| Phase | Description |
|---|---|
| Acute (<6 weeks) | Stable, injured AITFL +/- IOL, intact deltoid ligament Unstable, depends on other injuries including Latent diastasis, injured AITFL, deltoid ligament +/- IOL (MRI diagnosis) Frank diastasis, injured all syndesmotic ligaments and deltoid ligament (XR diagnosis) |
| Subacute | 6 weeks to 6 months |
| Chronic | >6 months |
Hawkins with Canale and Kelly (talar neck)
| Type | Description | Union | AVN |
|---|---|---|---|
| I | Undisplaced neck fracture | 100% | 0% |
| II | Subtalar subluxation or dislocation | 100% | 42% |
| III | Subtalar and ankle dislocation | 89% | 91% |
| IV | Type III with talonavicular subluxation or dislocation | 100% |
Sanders (calcaneus)
| Type | Description |
|---|---|
| I | ~All non-displaced articular fractures, irrespective of the number of fracture lines |
| II | ~two part fractures of the posterior facet, similar in appearance to a split fracture of the tibial plateau ~Three types, IIA, IIB & IIC exist, based on the location of the primary fracture line |
| III | ~three part fractures that feature a centrally depressed fragment, similar to a die punch type distal radial fracture ~Types include IIIAB, IIIAC & IIIBC |
| IV | ~highly comminuted ~often more than four articular fragments exist |
Eastwood (calcaneal lateral wall)
| Type | Lateral wall | Frequency |
|---|---|---|
| 1 | Formed by lateral joint fragment | 37% |
| 2 | Formed by lateral joint fragment superiorly & body fragment inferiorly | 45% |
| 3 | Formed by body fragment | 18% |
Myerson (Lisfranc)
| Type | Description |
|---|---|
| A | Total incongruity (lateral or dorsoplantar) |
| B1 | Partial incongruity, medial displacement of 1st MT |
| B2 | Partial incongruity, lateral displacement of other MT |
| C1 | Divergent displacement, partial |
| C2 | Divergent displacement, complete |
Original publication Myerson MS, Fisher RT, Burgess AR, Kenzora JE. Fracture dislocations of the tarsometatarsal joints: end results correlated with pathology and treatment. Foot Ankle. 1986;6(5):225-42.
Berndt and Harty (talar OCD)
| Stage | Description |
|---|---|
| 1 | Compression |
| 2 | Partially detached |
| 3 | Detached in its bed |
| 4 | Displaced |
| 5 (Loomer) | Subchondral cyst |
Original publication Berndt AL, Harty M. Transchondral fractures (osteochondritis dissecans) of the talus. J Bone Joint Surg Am. 1959;41-A:988-1020.
Hepple (talar OCD on MRI)
| Stage | Description |
|---|---|
| 1 | Cartilage damage only |
| 2a | Underlying fracture with oedema |
| 2b | Underlying fracture without oedema |
| 3 | Detached, undisplaced |
| 4 | Displaced |
| 5 | Subchondral cyst |
Original publication Hepple S, Winson IG, Glew D. Osteochondral lesions of the talus: a revised classification. Foot Ankle Int. 1999;20(12):789-93.
Coughlin and Shurnas (hallux rigidus)
| Grade | Dorsiflexion | Radiographs | Clinical |
|---|---|---|---|
| 0 | 40 to 60° (10 to 20% loss) | Normal | Stiffness only |
| 1 | 30 to 40° (20 to 50% loss) | Dorsal osteophyte, minimal joint narrowing | Mild or occasional pain and stiffness at extremes of motion |
| 2 | 10 to 30° (50 to 75% loss) | Mild to moderate narrowing, osteophytes, under a quarter of the dorsal head involved | Moderate to severe, more constant pain and stiffness |
| 3 | Under 10° (75 to 100% loss) | Severe narrowing, cysts, over a quarter of the dorsal head involved | Near constant pain, no pain in mid range |
| 4 | As grade 3 | As grade 3 | Pain in mid range of passive motion |
Original publication Coughlin MJ, Shurnas PS. Hallux rigidus. Grading and long-term results of operative treatment. J Bone Joint Surg Am. 2003;85(11):2072-88.
Tibialis posterior dysfunction
| Stage | Features | Management |
|---|---|---|
| I | Tenosynovitis, no deformity | Orthosis, immobilisation, tenosynovectomy |
| II | Flexible flatfoot | FDL transfer and medialising calcaneal osteotomy, with or without lateral column lengthening and spring ligament repair |
| III | Fixed hindfoot valgus | Triple arthrodesis |
| IV | Valgus tilt of the talus from deltoid failure | Triple or tibiotalocalcaneal arthrodesis, with deltoid reconstruction if the ankle is flexible |
Eichenholtz (Charcot foot)
| Stage | Phase | Description |
|---|---|---|
| 0 | Early | Joint oedema present, bone-scan positive, normal radiographs |
| 1 | Fragmentation | Maximal oedema, osseous fragmentation and joint dislocation |
| 2 | Coalescence | Oedema reducing, fragment coalescence and resorption of fine bone debris |
| 3 | Reconstruction | Oedema resolved, radiographic evidence of remodelling and consolidation of bone fragments |
Key reference (original not indexed in PubMed) Rosenbaum AJ, DiPreta JA. Classifications in brief: Eichenholtz classification of Charcot arthropathy. Clin Orthop Relat Res. 2015;473(3):1168-71.
Smillie (Freiberg disease)
| Stage | Features |
|---|---|
| I | Subchondral fissure fracture through the ischaemic epiphysis |
| II | Central bone resorption with early collapse of the articular surface |
| III | Further collapse with a central projection, plantar cartilage intact |
| IV | Fracture of the projection with loose body formation |
| V | Flattening and deformity of the head with arthrosis |
Coughlin (tailor bunionette)
| Type | Description |
|---|---|
| 1 | Enlarged fifth metatarsal head or lateral condyle |
| 2 | Lateral bowing of the fifth metatarsal shaft with a normal intermetatarsal angle |
| 3 | Increased fourth to fifth intermetatarsal angle, the most common |
Original publication Coughlin MJ. Treatment of bunionette deformity with longitudinal diaphyseal osteotomy with distal soft tissue repair. Foot Ankle. 1991;11(4):195-203.
Salter-Harris (physeal fractures)
| Type I | – Through the growth plate – More common in younger patients with thicker physis – Fast healing, rare to have complications |
| Type II | – *Most common type – Through growth plate and metaphysis, spares the epiphysis – Creates a separate metaphyseal fragment, called the ‘Thurston-Holland’ fragment – Fast healing |
| Type III | – Through growth plate and epiphysis, spares the metaphysis – Creates an intra-articular fracture – Requires anatomic reduction and internal fixation |
| Type IV | – Through growth plate, epiphysis and metaphysis – Possible growth disturbance and angular deformity – Requires anatomic reduction and internal fixation |
| Type V | – Rare – Compressive injury to the growth plate (e.g. crush injuries) – No associated fractures of the epiphysis or metaphysis – Possible permanent growth arrest |
Dias-Tachdjian (paediatric ankle)
| Supination-inversion |
| Supination plantarflexion |
| Supination-ER |
| Pronation-ER |
Gartland (supracondylar humerus)
| Type | Description |
|---|---|
| 1 | Undisplaced |
| 2a | Displaced with intact posterior cortex, angulation only |
| 2b | Displaced with intact posterior cortex, with rotation or translation |
| 3 | Completely displaced, no cortical contact |
Original publication Gartland JJ. Management of supracondylar fractures of the humerus in children. Surg Gynecol Obstet. 1959;109(2):145-54.
Jakob (lateral condyle)
| Stage | Description |
|---|---|
| 1 | articular surface is intact |
| 2 | into joint but no fracture fragment rotation |
| 3 | rotated & displaced |
Medial epicondyle and condyle fractures
| Type | Classification |
|---|---|
| I | Minimally displaced < 2 mm |
| II | Moderately displaced |
| III | Into joint |
| IV | Associated with a posterolateral dislocation of the elbow |
Meyers and McKeever (tibial eminence)
| Type | Description |
|---|---|
| I | Minimally displaced |
| II | Anterior elevation with a posterior hinge, a beak on the lateral film |
| IIIA | Complete separation of the ACL insertion only |
| IIIB | Complete separation of the entire eminence |
| IV | Comminuted (Zaricznyj) |
Original publication Meyers MH, McKeever FM. Fracture of the intercondylar eminence of the tibia. J Bone Joint Surg Am. 1959;41-A(2):209-20; discussion 220-2.
Ogden (tibial tubercle)
| Type | Description |
|---|---|
| IA | Elevation of distal part of tuberosity, minor anterior separation |
| IB | Elevation of distal part of tuberosity, separated from metaphysis &/or epiphysis |
| IIA | Separation of fragment from metaphysis & remainder of epiphysis (intra-articular extension). Tuberosity separated & anteriorly angulated |
| IIB | Separation of fragment from metaphysis & remainder of epiphysis (intra-articular extension). Tuberosity separated, anteriorly angulated & fragmented |
| IIIA | Major separation of fragment with intra-articular displacement. Fragment is unitary |
| IIIB | Major separation of fragment with intra-articular displacement. Fragment is comminuted |
Original publication Ogden JA, Tross RB, Murphy MJ. Fractures of the tibial tuberosity in adolescents. J Bone Joint Surg Am. 1980;62(2):205-15.
Triplane fractures
| Parts | Description |
|---|---|
| 2 part | Lateral & posterior epiphyseal fragment with posterior metaphyseal spike attached |
| 3 part | As described above |
| 4 part | Anterolateral & anteromedial epiphyseal fragments. Posterior epiphyseal fragment with posterior metaphyseal spike attached |
SUFE by timing
| Type | Presentation | Examination |
|---|---|---|
| Pre-slip | Lower limb weakness, limp and exertional groin, hip or knee pain. AP pelvis and frog leg lateral may show disuse osteopenia | Reduced internal rotation and guarding |
| Acute (10 to 15%) | Under 3 weeks, usually too painful to weight bear. Most have 1 to 3 months of prodromal knee, hip or thigh pain or limp | External rotation deformity, shortening and painful restricted motion |
| Chronic (about 85%) | Groin or thigh pain with a limp, with exacerbations and remissions over months to years | Antalgic gait, loss of internal rotation, abduction and flexion |
| Acute on chronic | Acute worsening of a chronic slip | As for an acute slip |
Loder (SUFE stability)
| Type | Definition | Osteonecrosis |
|---|---|---|
| Stable | Can weight bear, with or without crutches | Almost 0% |
| Unstable | Unable to weight bear, pain limits any attempt to move the limb | Up to 50% |
Original publication Loder RT, Richards BS, Shapiro PS, Reznick LR, Aronson DD. Acute slipped capital femoral epiphysis: the importance of physeal stability. J Bone Joint Surg Am. 1993;75(8):1134-40.
Herring lateral pillar (Perthes)
| Group | Description |
|---|---|
| A | Lateral pillar height fully preserved |
| B | Over 50% of lateral pillar height preserved |
| B/C border | Narrow or poorly ossified pillar near 50% |
| C | Under 50% of lateral pillar height preserved |
Original publication Herring JA, Neustadt JB, Williams JJ, Early JS, Browne RH. The lateral pillar classification of Legg-Calvé-Perthes disease. J Pediatr Orthop. 1992;12(2):143-50.
Stulberg (Perthes outcome)
| Class | Description |
|---|---|
| I and II | Spherical head, low arthritis risk |
| III and IV | Ovoid or flat congruent head |
| V | Flat head with incongruent joint, highest arthritis risk |
Original publication Stulberg SD, Cooperman DR, Wallensten R. The natural history of Legg-Calvé-Perthes disease. J Bone Joint Surg Am. 1981;63(7):1095-108.
Kocher criteria (septic hip)
| Criterion | Threshold |
|---|---|
| Non weight bearing | |
| Temperature | Over 38.5 degrees |
| ESR | Over 40 mm/h |
| WCC | Over 12 x 10^9/L |
| CRP (Caird) | Over 20 mg/L adds predictive value |
Langenskiold (Blount disease)
| Stage | Radiographic features |
|---|---|
| I | Irregular medial metaphyseal ossification with beaking |
| II | Saucer shaped depression of the medial metaphysis with a step |
| III | Deeper step with the medial epiphysis sloping into the defect |
| IV | Medial epiphysis fills the metaphyseal depression |
| V | Cleft dividing the medial epiphysis (double epiphysis) with articular depression |
| VI | Bony bar across the medial physis |
Original publication Langenskiöld A. Tibia vara; (osteochondrosis deformans tibiae); a survey of 23 cases. Acta Chir Scand. 1952;103(1):1-22.
Saupe (bipartite patella)
| Type | Location |
|---|---|
| I | Inferior pole |
| II | Lateral margin |
| III | Superolateral pole, the most common |
Clubfoot scoring (Pirani and Dimeglio)
| System | Description |
|---|---|
| Pirani score | Six clinical signs each scored 0, 0.5 or 1, total 0 to 6 |
| Dimeglio | Grades I to IV by reducibility, scored out of 20 |
Original publication Diméglio A, Bensahel H, Souchet P, Mazeau P, Bonnet F. Classification of clubfoot. J Pediatr Orthop B. 1995;4(2):129-36.
Coleman (vertical talus)
| Type | Description |
|---|---|
| 1 | Rigid dorsal dislocation of the talonavicular joint |
| 2 | Talonavicular dislocation with calcaneocuboid dislocation or subluxation |
Aitken (PFFD)
| Type | Description |
|---|---|
| A | Radiographic defect in the upper femur that later ossifies, femoral head & acetabulum form, varus deformity & shaft may be higher than the head |
| B | Tuft at proximal end of femur, never get connection between head & shaft (pseudoarthrosis), acetabulum & head are present, femur short |
| C | Absent femoral head, flat-absent acetabulum, short femur |
| D | As in C but with very short femur represented by femoral condyles |
Tibial hemimelia
| Type | Description |
|---|---|
| 1 | Tibia not seen at birth |
| 1a | upper tibia not present |
| 1b | upper tibia is late to ossify |
| 2 | Proximal tibia ossified, distal tibia absent |
| 3 | Distal tibia is ossified, proximal tibia absent |
| 4 | Congenital Diastases of the ankle |
Congenital pseudarthrosis of the tibia
| Type | Description |
|---|---|
| 1 Non-dysplastic | ~Increased cortical density ~Dense medullary canal |
| 2 Dysplastic | |
| a | ~Wide medullary canal ~Failure of tubulation |
| b | ~Cystic lesion before fracture or canal enlargement from a previous fracture |
| c | ~Fracture, Cysts & Frank pseudarthrosis; Narrowed ends of fragments |
Congenital lower limb deficiency
| Deficiency | Classification | Features |
|---|---|---|
| Fibular hemimelia | Achterman and Kalamchi | Most common long bone deficiency. Short tibia, anteromedial bowing, ball and socket ankle, tarsal coalition, absent lateral rays, ACL deficiency, genu valgum |
| Congenital femoral deficiency (PFFD) | Aitken, Paley | Short femur, coxa vara, hip instability, knee cruciate deficiency. Often associated with fibular hemimelia |
| Tibial hemimelia | Jones | Rare. Absent or deficient tibia with a prominent fibula |
Cleary and Omer (radioulnar synostosis)
| Type | Description |
|---|---|
| 1 | Fibrous synostosis with a normal, reduced radial head |
| 2 | Osseous synostosis with a normal, reduced radial head |
| 3 | Osseous synostosis with a hypoplastic, posteriorly dislocated radial head |
| 4 | Short osseous synostosis with an anteriorly dislocated, mushroom shaped radial head |
Original publication Cleary JE, Omer GE Jr. Congenital proximal radio-ulnar synostosis. Natural history and functional assessment. J Bone Joint Surg Am. 1985;67(4):539-45.
Brachial plexus birth palsy
| Type | Roots | Features | Frequency |
|---|---|---|---|
| Upper (Erb-Duchenne) | C5, C6 | Weak deltoid, external rotators, biceps, brachialis, brachioradialis and supinator. Waiter’s tip posture with the shoulder adducted and internally rotated, forearm pronated and wrist flexed. Minimal sensory loss, later elbow flexion contracture | Commonest |
| Complete | C5 to T1 | Flaccid paralysis of the whole limb, with or without vasomotor changes giving a marbled hand | Second most common |
| Lower (Klumpke) | C8, T1 | Weak wrist and long finger flexors and intrinsics. Poor hand function with good shoulder and elbow function | Least common |
GMFCS (cerebral palsy)
| Level | Description |
|---|---|
| 1 | Speed / balance and coordination are impaired, but patient is able to walk, play and climb stairs without need for railings |
| 2 | Speed, balance, coordination are all significantly impaired, patients may use gait aids (hand-held or wheelchair) depending on terrain and distance, will use railings for stairs and will have very limited running and jumping |
| 3 | Patients will utilise hand-held gait aids for most indoor movement, with wheeled mobility for outdoors and long distances, may self-propel for shorter distances. |
| 4 | Children use methods of mobility that require physical assistance or powered mobility in most settings. They may walk for short distances at home with physical assistance or use powered mobility or a body support walker when positioned. Outdoors / community mobility is in a manual wheelchair or powered mobility. |
| 5 | Totally dependent on assistance, wheelchair bound in all settings, limited ability to maintain antigravity head and trunk postures or control leg and arm movements |
Hoffer (spina bifida ambulation)
| Category | Description |
|---|---|
| Community ambulator | Walks indoors and outdoors with or without orthoses, wheelchair only for long trips or speed |
| Household ambulator | Walks only indoors with orthoses, independent or minimally assisted transfers, wheelchair outdoors |
| Non-functional ambulator | Walks only as therapy, wheelchair for mobility |
| Non-ambulator | Wheelchair bound, often able to transfer from bed to chair |
Original publication Hoffer MM, Feiwell E, Perry R, Perry J, Bonnett C. Functional ambulation in patients with myelomeningocele. J Bone Joint Surg Am. 1973;55(1):137-48.
Spina bifida neurosegmental level
| Level | Functioning muscles | Mobility |
|---|---|---|
| Thoracic | No voluntary lower limb function | Wheelchair |
| High lumbar (L1 to L3) | Hip flexors, with or without hip adductors and knee extensors | Children use HKAFO or KAFO, 75% of adolescents and adults use a wheelchair |
| Low lumbar (L4, L5) | As above plus knee extensors and flexors and ankle dorsiflexors, with or without hip abductors | 75% of adults are community ambulators, most with an AFO |
| Sacral (S1 to S4) | As above plus ankle plantarflexors, with or without toe flexors | Community ambulators for limited distances, with or without shoe orthoses |
Congenital kyphosis
| Type | Description |
|---|---|
| I | anterior failure of vertebral body formation |
| II | failure of segmentation |
| III | mixed |
| IV | unclassifiable because of its complexity |
SCIWORA
| Type | Description |
|---|---|
| Early | Acute diagnosis, about 50% of cases |
| Delayed | Onset after a latent period of 1 to 4 days |
| Recurrent | A second episode 3 days to 10 weeks later, in about 15% of cases |
Staheli rotational profile
| Measure | Normal |
|---|---|
| Foot progression angle | 5° ± 10° |
| Thigh foot angle | 15° ± 15° |
| Hip internal and external rotation | 45° ± 15° each |
| Transmalleolar axis | 0 to 30° external rotation |
Original publication Staheli LT, Corbett M, Wyss C, King H. Lower-extremity rotational problems in children. Normal values to guide management. J Bone Joint Surg Am. 1985;67(1):39-47.
Siffert (osteochondroses)
| Type | Description | Examples |
|---|---|---|
| Articular | Joint surface and epiphysis, with risk of secondary osteoarthritis | Perthes, Freiberg, Kohler, Panner |
| Non-articular | Traction apophysitis at a tendon or ligament insertion, self-limiting | Osgood-Schlatter, Sever, Sinding-Larsen-Johansson |
| Physeal | Growth plate involvement with resulting deformity | Blount, Scheuermann |
Original publication Siffert RS. Classification of the osteochondroses. Clin Orthop Relat Res. 1981;(158):10-8.
Enneking (benign tumours)
| Stage | Behaviour | Examples |
|---|---|---|
| 1 Latent | Grows, then stops, with a tendency to spontaneous resolution | Non ossifying fibroma, lipoma |
| 2 Active | Progressive growth, excision leaves tumour in the reactive zone | Aneurysmal bone cyst |
| 3 Aggressive | Locally aggressive, extends through the capsule into the reactive zone, does not metastasise | Giant cell tumour, desmoid |
Enneking (malignant tumours)
| Stage | Grade | Site |
|---|---|---|
| IA | Low | Intracompartmental |
| IB | Low | Extracompartmental |
| IIA | High | Intracompartmental |
| IIB | High | Extracompartmental |
| III | Any grade with metastasis | Any |
Original publication Enneking WF, Spanier SS, Goodman MA. A system for the surgical staging of musculoskeletal sarcoma. Clin Orthop Relat Res. 1980;(153):106-20.
Enneking surgical margins
| Margin | Description |
|---|---|
| Intralesional | Plane through tumour, as in curettage |
| Marginal | Through the reactive zone, which may hold satellite cells |
| Wide | Tumour with reactive zone and normal cuff, skip lesions possible |
| Radical | Entire compartment removed |
Original publication Enneking WF, Spanier SS, Goodman MA. A system for the surgical staging of musculoskeletal sarcoma. Clin Orthop Relat Res. 1980(153):106-20.
| Variable | 1 | 2 | 3 |
|---|---|---|---|
| Site | Upper limb | Lower limb | Peritrochanteric |
| Pain | Mild | Moderate | Functional |
| Lesion | Blastic | Mixed | Lytic |
| Size | Under one third | One third to two thirds | Over two thirds |
Original publication Mirels H. Metastatic disease in long bones. A proposed scoring system for diagnosing impending pathologic fractures. Clin Orthop Relat Res. 1989(249):256-64.
SINS (spinal instability)
| Score | Category |
|---|---|
| 0 to 6 | Stable |
| 7 to 12 | Potentially unstable |
| 13 to 18 | Unstable |
Lodwick (lytic patterns)
| Grade | Description |
|---|---|
| IA | Geographic with sclerotic rim |
| IB | Geographic, well defined, no sclerotic rim |
| IC | Geographic with ill defined margin |
| II | Moth-eaten |
| III | Permeative |
Original publication Lodwick GS, Wilson AJ, Farrell C, Virtama P, Dittrich F. Determining growth rates of focal lesions of bone from radiographs. Radiology. 1980;134(3):577-83.
Campanacci (giant cell tumour)
| Grade | Description |
|---|---|
| 1 | Intramedullary lesion confined to bone |
| 2 | Thinned, expanded cortex |
| 3 | Cortical breakout |
Aneurysmal bone cyst
| Type | Description |
|---|---|
| Primary | Arise de novo |
| Secondary | Arise in pre-existing tumours, frequently GCTs. More than 50% of ABCs arise from preexisting lesions |
Simple bone cyst
| Type | Description |
|---|---|
| A: Active | usually juxta-epiphyseal |
| B: Inactive | cyst lies nearer the diaphysis (is more than 2cm removed from the physis) Inactive cysts are less aggressive & more amenable to treatment |
Osteosarcoma by anatomy
| Type | Subtypes |
|---|---|
| 1. Central | Further subclassified by grade (high grade, 10-20yo, most common, or low grade) and pathology (conventional, telangiectatic, small cell, giant cell) |
| 2. Juxtacortical (surface osteosarcoma) | Low grade (30-40yo, usually low grade) or high grade Parosteal or Periosteal |
| 3. Intra-cortical | |
| 4. Soft tissue | |
| 5. Secondary |
Chondrosarcoma types
| Type | Description |
|---|---|
| Primary | Arise de novo, most |
| Secondary, from pre-existing cartilage lesions | Osteocartilaginous exostosis Enchondroma (Ollier disease, Maffucci syndrome) Periosteal chondroma Chondroblastoma Chondromyxofibroma Synovial chondromatosis Earlier age of presentation than the primary tumours |
| Secondary, from other cause | Pagets Radiation Later presentation than the primary tumours |
Lipomatous tumours
| Tumour | Features |
|---|---|
| Lipoma | Most common soft tissue tumour, superficial, soft and mobile |
| Intramuscular lipoma | Deep, may infiltrate muscle |
| Atypical lipomatous tumour | Deep and large, MDM2 amplification, local recurrence without metastasis |
| Myxoid liposarcoma | Metastasises to unusual sites such as spine and retroperitoneum. Whole spine MRI for staging |
| Dedifferentiated and pleomorphic liposarcoma | High grade, metastatic potential |
Cierny-Mader (osteomyelitis anatomy)
| Anatomic type | Description |
|---|---|
| I | Medullary, endosteal disease confined to the medullary canal |
| II | Superficial, contiguous infection of the outer cortex beneath a soft tissue defect |
| III | Localised, full thickness cortical sequestration that can be excised without loss of stability |
| IV | Diffuse, permeative disease with mechanical instability before or after debridement |
Cierny-Mader (host)
| Host | Description |
|---|---|
| A | Healthy host with normal physiological, metabolic and immune function (for example WCC over 1,500/mm3, albumin over 3.5 g/dL, protein over 6 g/dL, ferritin 10 to 200 ng/mL, transferrin under 200 mg/dL) |
| B | Local or systemic compromise, or both |
| C | Severe compromise, treatment worse than the disease, not a surgical candidate |
Original publication Cierny G 3rd, Mader JT, Penninck JJ. A clinical staging system for adult osteomyelitis. Clin Orthop Relat Res. 2003;(414):7-24.
Tsukayama (periprosthetic infection)
| Type | Description |
|---|---|
| Early postoperative | Within about four weeks |
| Acute haematogenous | Sudden onset in a well functioning joint |
| Chronic | Insidious onset beyond four weeks |
| Positive intraoperative cultures | Positive cultures at presumed aseptic revision |
Original publication Tsukayama DT, Estrada R, Gustilo RB. Infection after total hip arthroplasty. A study of the treatment of one hundred and six infections. J Bone Joint Surg Am. 1996;78(4):512-23.
CRPS stages
| Stage 1 | Stage 2 | Stage 3 | |
|---|---|---|---|
| Acute | Dystrophic | Atrophic | |
| Time | 0-3/12 | 3-6/12 | > 6/12 |
| Symptoms | Continued localised pain Aggravated by stress | Proximal spread of pain | Intractable pain |
| Signs | Skin changes Swollen & warm sensory – allodynia autonomic – wet with excess swelling motor – joints have decreased ROM | Skin changes Cool & dry Mottled & dusky Atrophic with shininess & decreased hair Oedema of limb | Atrophy of skin, muscles & bone Flexion contractures |
| Investigations | XR: normal Bone scan +ve with Periarticular accentuation on delayed scan Highly specific Not predictive | XR: Early osteoporosis | XR: Narrow joint space Diffuse osteoporosis |
Cook and Purdam (tendinopathy)
| Stage | Description |
|---|---|
| Reactive | Thickened tendon with intact collagen, reversible with load reduction |
| Disrepair | Matrix breakdown and early neovascularity |
| Degenerative | Cell death and disordered matrix, prone to rupture |
Original publication Cook JL, Purdam CR. Is tendon pathology a continuum? A pathology model to explain the clinical presentation of load-induced tendinopathy. Br J Sports Med. 2009;43(6):409-16.
ACR 1987 (rheumatoid arthritis)
| Criterion | Requirement |
|---|---|
| Morning stiffness | > 1 hour |
| Symmetrical arthritis | > 6/52 |
| Arthritis affecting 3 joints or more | > 6/52 |
| Arthritis of hand | > 6/52 |
| Rheumatoid nodules | Present |
| Rheumatoid factor | Positive |
| Radiological changes | Present |
Ankylosing spondylitis criteria
| Requirement | Criteria |
|---|---|
| Required | Positive XR sacroiliitis |
| Plus one or more | History of lumbar spine pain Stiff lumbar spine Chest expansion < 1″ at 4th intercostal space |
CPPD
| Type | Notes |
|---|---|
| Idiopathic chondrocalcinosis | By far the most common. Pseudorheumatoid arthritis with continuous attack, pseudo osteoarthritis with acute attacks, pseudo osteoarthritis without acute attacks, lanthanic (asymptomatic) |
| Hereditary | |
| Secondary (“WHIP A DOG”) | Wilson’s, haemochromatosis, hyperparathyroidism, hypothyroidism, hypophosphatasia, idiopathic, pseudogout, pernicious anaemia, acromegaly, diabetes, degenerate, ochronosis (alkaptonuria), gout |
Haemophilia severity
| Factor level | Bleeding risk |
|---|---|
| > 50% | Normal |
| 25-50% | Seldom a problem |
| 5-25% | Severe bleed with surgery (mild) |
| 1-5% | Severe bleed with minor injury (moderate) |
| < 1% | Spontaneous bleed (severe) |
Haemophilic arthropathy (radiological)
| Stage | Description |
|---|---|
| 1 | Acute haemarthrosis Soft tissue swelling |
| 2 | Subacute haemarthrosis Epiphyseal osteoporosis Epiphyseal overgrowth |
| 3 | No significant narrowing of joint Squaring of patella Enlarged femoral condyles Widened intercondylar notch in knee Widened trochlear notch at elbow |
| 4 | Marked narrowing of joint space |
| 5 | Joint destruction Mimics RA / TB |
Ehlers-Danlos 2017
| Type | Features |
|---|---|
| Hypermobile | Most common, no identified gene |
| Classical | COL5A1 or COL5A2 mutations |
| Vascular | COL3A1 mutations |
| Kyphoscoliotic | PLOD1 or FKBP14 mutations |
Neurofibromatosis
| Type | Features |
|---|---|
| NF 1 | 2 or more of the National Institute of Health criteria At least 6 café au lait spots (> 5mm in children, > 15 mm in adults) 2 neurofibromas or 1 plexiform neurofibroma Freckling of the inguinal or axillary region Optical glioma At least 2 Lisch nodules (iris condensations / hamartoma of the iris) A first degree relative with NF A distinctive osseous lesion (sphenoid dysplasia, thinning of long bone cortex with or without pseudarthrosis) |
| NF 2 | Bilateral acoustic neuromas (bilateral vestibular schwannomas). Paucity of peripheral findings |
Wynne-Davies (ligamentous laxity)
| Joint | Laxity |
|---|---|
| Thumb | Touching forearm on flexing wrist |
| Fingers | Parallel to forearm with wrist extension |
| Elbows | Extend past 180° |
| Knees | Extend past 180° |
| Foot | Dorsiflex past 45° |
Muscular dystrophy
| Inheritance | Types |
|---|---|
| X linked | Duchenne, Becker, Emery-Dreifuss |
| Autosomal recessive | Limb girdle, infantile facioscapulohumeral |
| Autosomal dominant | Facioscapulohumeral, distal, ocular, oculopharyngeal |
Use the up and down arrow keys to move through the classifications. In Test me mode, press space to show the answer.
Browse by category
- Classifications of Adult Trauma & Fractures
- Classifications of Adult Elective Orthopaedic Disorders
- Classifications of Paediatric Trauma & Fractures
- Classifications of Paediatric Elective Orthopaedic Disorders
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.