
Overview
- Narrowing of the central canal, lateral recess or foramina
- Disc bulge, facet hypertrophy and ligamentum flavum thickening, sometimes with degenerative spondylolisthesis
- Neurogenic claudication, buttock and leg pain on walking relieved by sitting or flexion
- Distinguish from vascular claudication
- MRI is the investigation of choice
- Many improve or stay stable with physiotherapy and analgesia
- Decompression, with or without fusion, gives good results for leg symptoms
Western Health Orthopaedic Registrar presentation – Lumbar Canal Stenosis By Dr Glenn Gomez
Anatomy
- Lateral recess stenosis compresses the traversing root (L5 at L4/5)
- Foraminal stenosis compresses the exiting root (L4 at L4/5)
Aetiology
- Degenerative is most common, with disc bulge, facet hypertrophy and ligamentum flavum buckling
- Degenerative spondylolisthesis, most often at L4/5
Classification
Schizas (axial T2 MRI)
| Grade | Description |
|---|---|
| A | CSF clearly visible |
| B | Rootlets fill the sac but can be individualised |
| C | No CSF, rootlets indistinguishable, posterior fat present |
| D | No CSF and no posterior epidural fat |
- C and D are severe and more often fail non-operative care
Clinical Features
- Relief with sitting or flexion (shopping trolley sign), uphill better than downhill, cycling tolerated
- Vascular claudication gives calf pain relieved by standing still, absent pulses and pain on cycling
Investigations
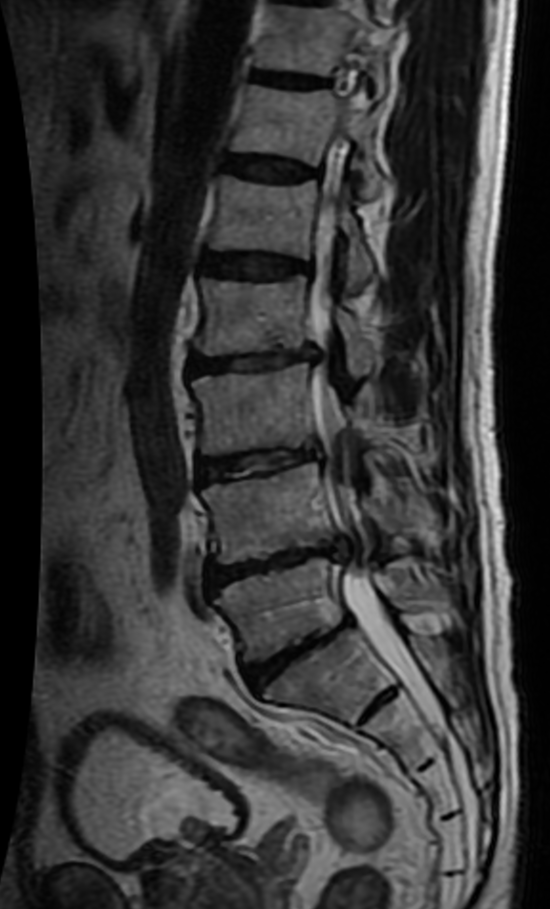
- Flexion and extension films for dynamic instability
- MRI is the investigation of choice, CT myelography if contraindicated
Management
- LESS trial found little benefit of epidural steroid over local anaesthetic
- Decompression preserves the pars and half of each facet
- SPORT favoured surgery in the as-treated analysis
- Swedish Spinal Stenosis Study found no benefit from adding fusion
- SLIP found a modest fusion advantage in stable grade 1 spondylolisthesis
- NORDSTEN-DS found decompression alone non-inferior
- Fusion for dynamic instability, deformity or wide facetectomy
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.