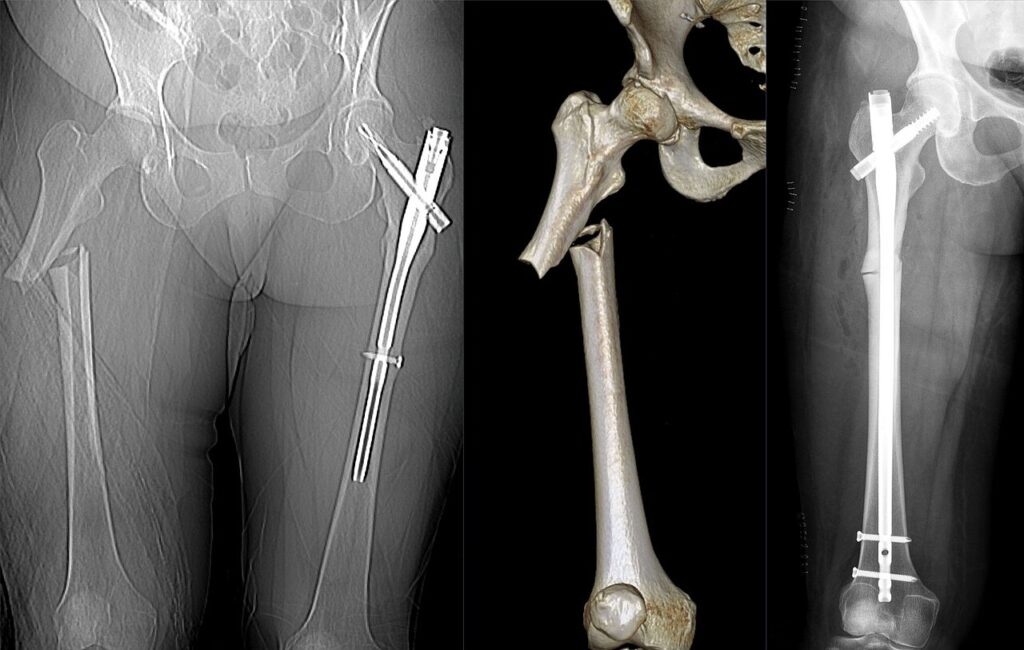
Subtrochanteric femur fractures lie between the lesser trochanter and a point 5 cm distal to it. Strong deforming forces flex, abduct and externally rotate the proximal fragment, so reduction is difficult. Most are fixed with a long cephalomedullary nail, and atypical fractures from bisphosphonate use should be considered in older patients.
Definition
Fracture between the lesser trochanter and a point 5 cm distal to it
Fracture lines can extend proximally into the greater trochanter or piriformis fossa
Incidence
Bimodal distribution, young adults with high energy and elderly with low energy injury
Atypical fractures linked with long term bisphosphonate use
Subtrochanteric region is a common site of pathological fracture
Aetiology
High energy trauma in young adults
Low energy falls in osteoporotic elderly
Pathological fracture from metastases
Atypical femoral fracture with prolonged bisphosphonate or denosumab use
Iatrogenic stress riser below a screw entry hole or DHS
Anatomy
High compressive stress medially and tensile stress laterally
Mostly cortical bone with slower healing than metaphyseal bone
Proximal fragment flexed by iliopsoas
Proximal fragment abducted by gluteus medius and minimus, externally rotated by short rotators
Distal fragment adducted and shortened by adductors and hamstrings
Classification Type Description I fracture is at the level of the lesser trochanter II fracture is 2.5 to 5 cm below the lesser trochanter III fracture is 5 to 7.5 cm below the lesser trochanter
Fielding’s Classification of Subtrochanteric Fractures Transverse fractures fit this classification well, but oblique and comminuted fractures may involve more than one of the levels described Type Description I Nondisplaced fracture or one with less than 2 mm of displacement II Two-part fracture IIa Transverse fracture IIb Spiral configuration with the lesser trochanter attached to proximal fragment IIc Spiral configuration with the lesser trochanter attached to distal fragment III Three-part fracture IIIa Three-part spiral configuration with the lesser trochanter a part of the third fragment IIIb Three-part spiral configuration with the third part a butterfly fragment IV Comminuted fracture with four or more fragments V Subtrochanteric-intertrochanteric configuration
Seinsheimer classification of Subtrochanteric Fracturesbased on involvement of piriformis fossa Type Description I fracture does not extend into piriformis fossa Ia comminution and fracture lines extend from below lesser trochanter to femoral isthmus Ib fracture lines and comminution involve area of lesser trochanter to isthmus II fracture extends proximally into greater trochanter and involves piriformis fossa IIa no significant comminution or fracture of lesser trochanter IIb significant comminution of medial femoral cortex and loss of continuity of lesser trochanter
Russell-Taylor classification of subtrochanteric fracture of femur Pathology
Medial cortical comminution leads to varus collapse and implant failure
Atypical fractures start as a lateral cortical stress reaction with beaking
Atypical fractures are transverse or short oblique with a medial spike
High energy injuries show comminution and soft tissue injury
History
Mechanism and energy of injury
Prodromal thigh pain in atypical or pathological fractures
Bisphosphonate or denosumab use and duration
History of malignancy
Comorbidities, premorbid mobility and residence
Examination
ATLS assessment in high energy injuryShortened, externally rotated and swollen thigh
Distal neurovascular status
Skin for open wounds
Contralateral thigh tenderness suggesting bilateral atypical fracture
Investigations Imaging of an atypical subtrochanteric femoral fracture associated with bisphosphonate therapy. Image by Hellerhoff, Wikimedia Commons , CC BY-SA 4.0 .
AP pelvis and full length femur AP and lateral
Include the hip and knee joints
Traction view helps define the fracture pattern
Contralateral femur in atypical fractures to look for lateral cortical beaking
CT if piriformis fossa extension or comminution is unclear
Treatment
Rarely indicated in adults
Reserved for patients unfit for anaesthesia
90 90 skeletal traction historically used, with high complication rates
Recumbency causes pressure injury, VTE and pneumonia
Malunion into varus, shortening and malrotation
Treatment Recommendations Based on Russell-Taylor Classification of Subtrochanteric Fractures
Type Fracture Description Treatment Ia Piriformis fossa and lesser trochanter intact Standard interlocking IM nail Ib Piriformis fossa intact, lesser trochanter fractured Reconstruction IM nail IIa Piriformis fossa fractured, lesser trochanter intact Hip screw or reconstruction IM nail IIb Piriformis fossa and lesser trochanter fractured Hip screw with bone graft or reconstruction IM nail
Treatment Recommendations Based on Russel-Taylor Classification of Subtrochanteric Fractures Complications Prognosis
Most unite with nailing and accurate reduction
Varus malreduction over 10 degrees is associated with nonunion
Atypical fractures heal slowly with higher nonunion rates
Elderly patients have mortality similar to other hip fractures
Reviewed by Professor Phong Tran , Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.
Next Dislocated Hip