
Epidemiology
- Congenitally abnormal meniscus
- Affects 1% of all lateral menisci
- Only 3% of all discoid menisci are medial
- Caused by abnormal formation of fibrocartilage in the mesenchyme
Pathology
- Different types, variety of pathology, combinations of:
- Lateral meniscotibial ligaments are absent, meniscus isn’t attached to tibial plateau
- Meniscofemoral fibres are present
- Ligament of Wrisberg attaches to PCL
- Peripheral meniscus is thickened
- Covers all or part of the plateau
History
- often presents as a “snapping knee”
- bilateral lateral discoid menisci in 20 %
- Usually presents around age 8
- Snapping, shift of tibial plateau
- Visible/palpable mass, prominent anterolaterally with flexion, reduces with extension
- May become associated with osteochondritis dissecans
- Complete and incomplete types (see below)
- Present as per meniscal tear
- Often “young” for a meniscal tear – 14-16
Investigations
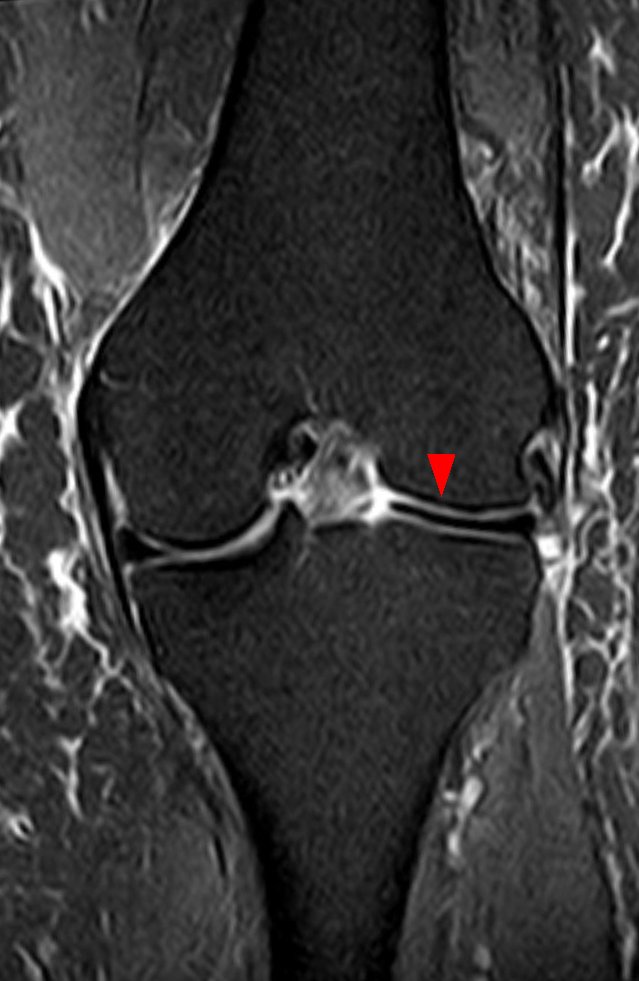
- may have widened joint space
- MRI indicated most of the time
Classification
Watanabe
| Type | Description | Treatment of symptomatic tears |
|---|---|---|
| 1 Complete (stable), most common | Discoid meniscus covers tibial plateau. Lateral ligaments are intact, therefore stable | Saucerization to stable peripheral rim of 6-8 mm |
| 2 Incomplete | Similar to complete, covers less of the plateau | Saucerization to stable peripheral rim of 6-8 mm |
| 3 Wrisberg ligament type (unstable) | Deficiency of posterior horn meniscal tibial ligaments. Unstable and hypermobile posterior horn. On knee extension, abnormal meniscus is pulled posteromedially into the intercondylar notch (instead of gliding forward) due to the action of the meniscofemoral ligaments. Probably responsible for the true “snapping knee” | Try to repair to reattach the posterior horn. Meniscectomy may be needed since it lacks posterior meniscal tibial attachments & has unstable posterior horn. Meniscal transplant not yet shown to be effective in skeletally immature patients |
Treatment
- If asymptomatic, incidental finding, not recommended to treat
- Total meniscectomy is associated with 75% rate of degenerative tear
- Contouring or sculpting of meniscal tissue is hopeful procedure, but no long term studies to advocate
- Minor tears may heal, may need partial excision, repair
- Treatment of the Wrisberg type is most challenging:
- Thickness of cartilage rim can lead to recurrent snapping
- Techniques for reattachment, contouring are still evolving
- Meniscal transplant as a teenager may be best solution
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.