
Indications
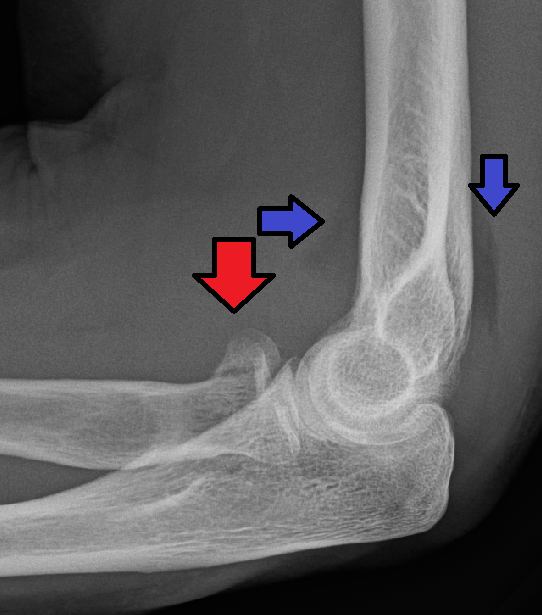
- Comminuted radial head fractures that cannot be reconstructed, more than three fragments
- Fractures with elbow instability, terrible triad and Essex-Lopresti injuries
- Mason type III fractures where fixation would be unstable
- Radial head excision alone is avoided when the elbow or forearm is unstable
Position
- Supine with arm table, or lateral
- Image intensifier available
- Tourniquet
Operative Steps
- Kocher interval between ECU and anconeus, or Kaplan interval between EDC and ECRB
- Keep the forearm pronated to move the posterior interosseous nerve away
- Protect the lateral ulnar collateral ligament
- Excise fragments and reassemble them to size the implant, choosing smaller if between sizes
- Neck cut perpendicular to the shaft
- Trial and avoid overstuffing. Lateral ulnohumeral joint space should match the medial
- Repair the lateral ligament complex to the epicondyle
- Radiographs and fluoroscopy check the ulnohumeral joint for gapping
- Monopolar or bipolar implants with smooth or porous stems
- Repair the coronoid and medial structures when part of a terrible triad
Postoperative Care
- Early protected motion
- Splint for instability patterns
- Hinged brace for instability patterns
- Rehabilitation over 3 months
Complications
- Overstuffing causing capitellar wear and stiffness
- Loosening and painful stem
- Posterior interosseous nerve palsy
- Persistent instability
- Loosening of the stem
- Heterotopic ossification
- Posterior interosseous nerve palsy
Related Pages
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.