
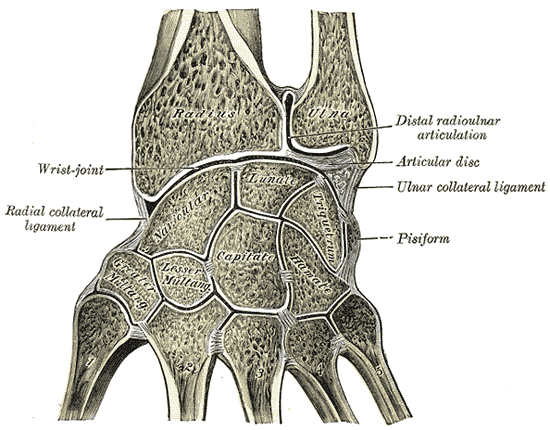
Indications
- Septic arthritis of the radiocarpal or midcarpal joint failing aspiration or arthroscopic lavage.
- Loculated pus or debris needing open debridement.
- Carpal osteomyelitis requiring drainage.
- Arthroscopic wrist lavage is an alternative in early infection.
Position
- Supine with the arm on a hand table and the forearm pronated.
- Upper arm tourniquet.
Landmarks and Incision
- Palpate Lister tubercle and the radiocarpal joint line.
- Make a longitudinal dorsal incision of about 5 cm centred over Lister tubercle.
Superficial Dissection
- Preserve dorsal veins and branches of the superficial radial nerve.
- Incise the extensor retinaculum over the third compartment and release extensor pollicis longus (EPL).
- Retract EPL radially and the fourth compartment tendons ulnarly.
Deep Dissection
- Identify the posterior interosseous nerve on the floor of the fourth compartment.
- Excise or protect the nerve as required.
- Berger ligament-sparing capsulotomy raises a radially based flap along the dorsal radiocarpal and intercarpal ligament fibres.
- Alternatively open the capsule longitudinally for a septic wrist. Irrigate and debride synovium and fibrin.
- Inspect the scapholunate ligament and carpal cartilage.
- Leave the capsule open or loosely closed over a drain. Leave EPL transposed out of the third compartment.
Structures at Risk
- EPL, which ruptures when left in a closed compartment.
- Superficial radial nerve branches.
- Posterior interosseous nerve.
- Scapholunate ligament and dorsal radiocarpal ligament.
Extension
- Extend proximally along the fourth compartment and distally to the carpometacarpal joints.
- A volar approach drains volar sepsis.
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 20 October 2026.