
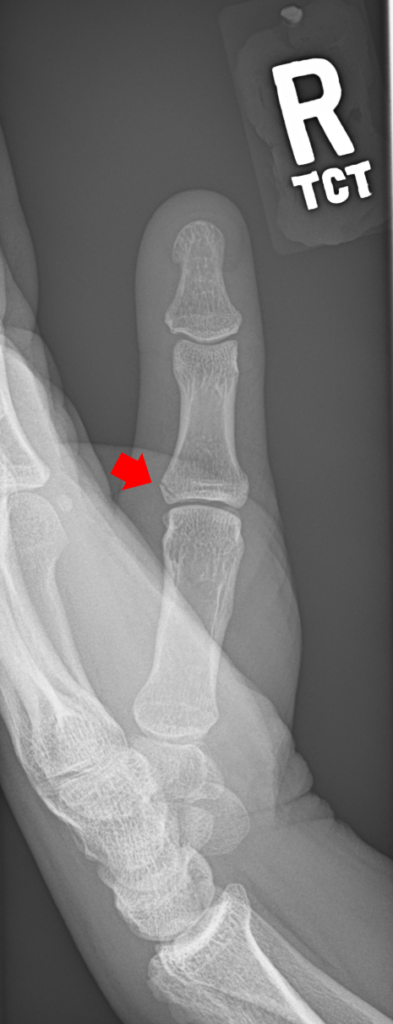
Indications
- Complete rupture with laxity over 35 degrees, or 15 degrees more than the other side, in 30 degrees flexion
- No firm endpoint
- Stener lesion, adductor aponeurosis trapped between ligament and bone
- Displaced or rotated bony avulsion
- Partial tears with a firm endpoint are treated in a thumb spica for 4 to 6 weeks
- Chronic instability needs ligament reconstruction with a tendon graft or MCP fusion
Position
- Supine, hand table, tourniquet
- Image intensifier for bony avulsions
Operative Steps
- Curved dorsoulnar incision over the MCP joint
- Protect branches of the superficial radial nerve
- Incise the adductor aponeurosis to find the ligament
- Reattach the ligament to the proximal phalanx base with a suture anchor
- Fix large bony fragments with a screw or anchor
- Repair the adductor aponeurosis
- A Stener lesion appears as a lump proximal to the adductor aponeurosis
- Check stability through range before closure
- K wire across the MCP joint if repair is tenuous
Postoperative Care
- Thumb spica splint for 4 to 6 weeks
- Avoid pinch loading for 3 months
- Hand therapy for motion from about 4 weeks
- Return to contact sport with protection at about 3 months
Complications
- Superficial radial nerve injury
- Stiffness
- Persistent instability
- Anchor pull out
- Arthritis of the MCP joint in chronic cases
- Complex regional pain syndrome
Related Pages
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.