
Question
A 70 year old woman with breast cancer has 6 weeks of thigh pain on walking. A radiograph shows a 3 cm lytic lesion in the subtrochanteric femur involving more than half of the cortex.
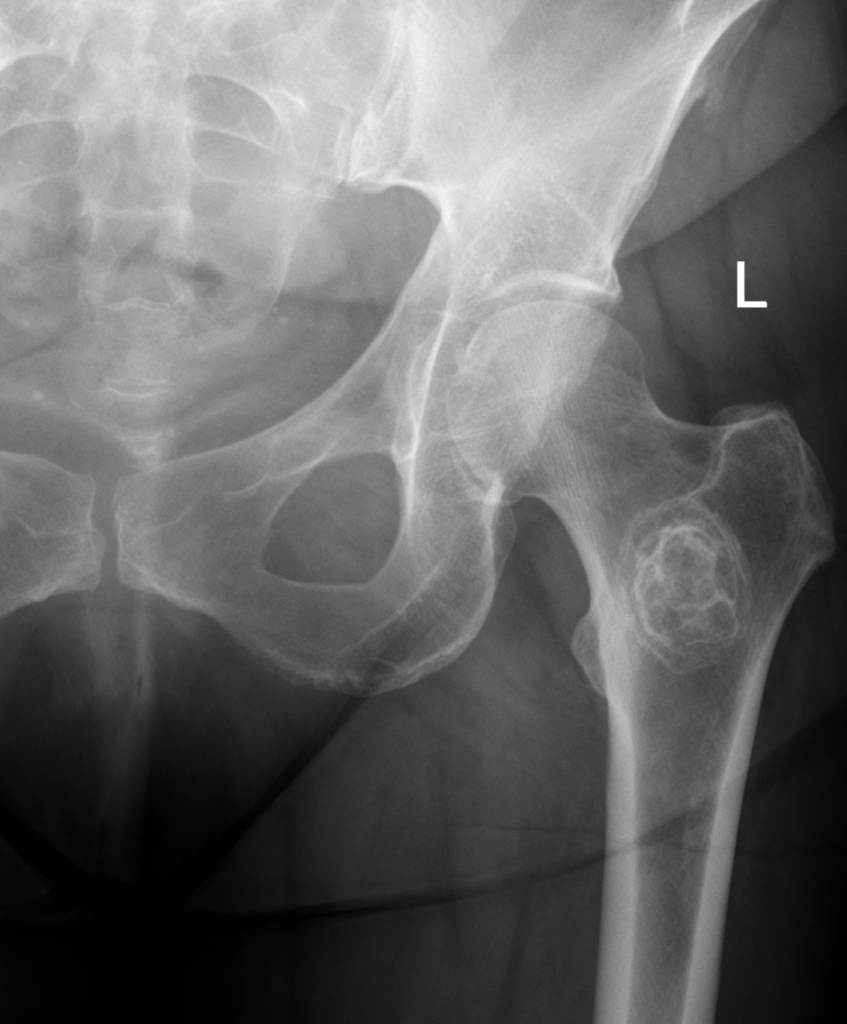
- How would you assess fracture risk?
- What investigations are needed before surgery?
- What are your surgical principles?
Answer
Assessing fracture risk
| Mirels | 1 | 2 | 3 |
|---|---|---|---|
| Site | Upper limb | Lower limb | Peritrochanteric |
| Pain | Mild | Moderate | Functional |
| Lesion | Blastic | Mixed | Lytic |
| Size (cortex) | Under 1/3 | 1/3 to 2/3 | Over 2/3 |
Interpretation
- A Mirels score of 9 or more suggests prophylactic fixation, and this patient scores 11 or 12
- Axial cortical involvement over 30 mm on CT is another indicator
Investigations
- Full length femoral radiographs and imaging of the whole bone
- Staging CT and bone scan, and review of oncology history
- Biopsy if this is a solitary lesion or the first metastasis, to exclude a primary sarcoma
- Calcium and FBC, and embolisation for vascular metastases such as renal and thyroid
Surgical principles
- Protect the whole femur with a long cephalomedullary nail
- Vent the canal and ream gently to reduce fat embolism
- Cemented long stem arthroplasty if the head or neck is involved
- Postoperative radiotherapy to the whole operated field
- Bisphosphonate or denosumab to reduce skeletal events
Related pages
Author Contributions
Orthofracs team
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.