
Overview
- Far more common than malignant tumours, often incidental
- Age, location in the bone and radiographic appearance narrow the differential
- Well defined, sclerotic margin and no soft tissue mass suggest benign
- Enneking stages latent, active and aggressive
- Observe latent lesions
- Discuss atypical lesions with a sarcoma service before biopsy
Western Health Orthopaedic Registrar presentation – Benign Bone Lesions by Dr Jack Pang
Western Health Orthopaedic Registrar presentation – Benign Bone Tumours By Dr Daniel Sydenham
Classification
Enneking benign staging
| Stage | Description | Treatment |
|---|---|---|
| 1 | Latent | Observation |
| 2 | Active | Intralesional curettage |
| 3 | Aggressive, cortical breach | Extended curettage with adjuvant or en bloc excision |
Pathology
- Osteoid osteoma is under 1.5 cm with NSAID-responsive night pain, treated by radiofrequency ablation
- Osteoblastoma exceeds 2 cm, favours posterior spinal elements and can be locally aggressive
- Enchondroma versus chondrosarcoma relies on pain, scalloping beyond two thirds, cortical breach and size
- Ollier disease and Maffucci syndrome carry increased malignant risk
- Osteochondroma is the commonest benign bone tumour, with continuous cortex and medulla
- An adult cartilage cap over about 2 cm suggests secondary chondrosarcoma
- Multiple hereditary exostoses relate to EXT1 and EXT2
- Chondroblastoma is epiphyseal in immature patients, with chicken-wire calcification
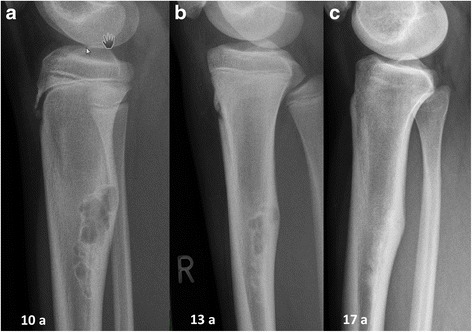
- NOF resolves spontaneously, with multiple lesions in Jaffe-Campanacci syndrome
- Fibrous dysplasia has GNAS mutation, ground glass and shepherd’s crook deformity
- UBC shows the diagnostic fallen fragment sign
- ABC has fluid-fluid levels and USP6 rearrangement, so exclude telangiectatic osteosarcoma
- GCTB is epimetaphyseal after maturity, H3F3A mutated and RANKL driven
- LCH gives vertebra plana, with CD1a positivity and Birbeck granules
Management
- Biopsy uncertain lesions following sarcoma principles
- Phenol, liquid nitrogen, argon beam or burr adjuvants reduce recurrence
- Denosumab for unresectable GCTB
- Fibrous dysplasia needs internal fixation, as graft is resorbed
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.