
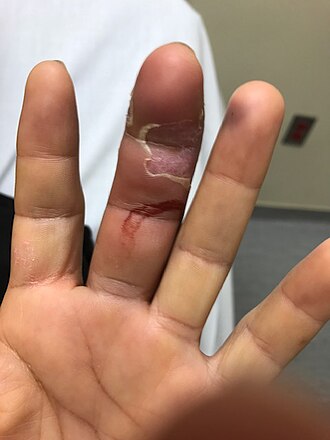
Indications
- Pyogenic flexor tenosynovitis, Kanavel signs
- Failure to improve within 24 hours of IV antibiotics
- Kanavel signs are fusiform swelling, flexed posture, tenderness along the sheath and pain on passive extension
- Early cases within 24 hours may settle with IV antibiotics, elevation and splinting
- Diabetes, immunosuppression and delayed presentation favour early surgery
Position
- Supine, arm table, tourniquet without exsanguination
Operative Steps
- Proximal incision over the A1 pulley to open the sheath
- Distal incision at the A5 pulley, midaxial or distal palmar
- Pass a fine catheter into the sheath proximally
- Irrigate with saline until clear from the distal incision
- Send fluid for culture, leave incisions open or loosely closed
- Open washout through a Bruner or midaxial incision for advanced infection with necrotic tissue
- Protect the neurovascular bundles and preserve the A2 and A4 pulleys
- Avoid high pressure irrigation that tracks into soft tissue
Postoperative Care
- IV antibiotics, elevation and early motion
- Repeat washout if not improving
- Hand therapy within 24 to 48 hours to limit adhesions
- Tailor antibiotics to cultures, Staph aureus is the usual organism
- Review the wound daily for spreading infection
Complications
- Tendon necrosis and adhesions
- Stiffness
- Amputation in delayed diabetic cases
- Spread to the deep palmar spaces or a horseshoe abscess
- Boutonniere or swan neck deformity from tendon loss
Related Pages
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.