
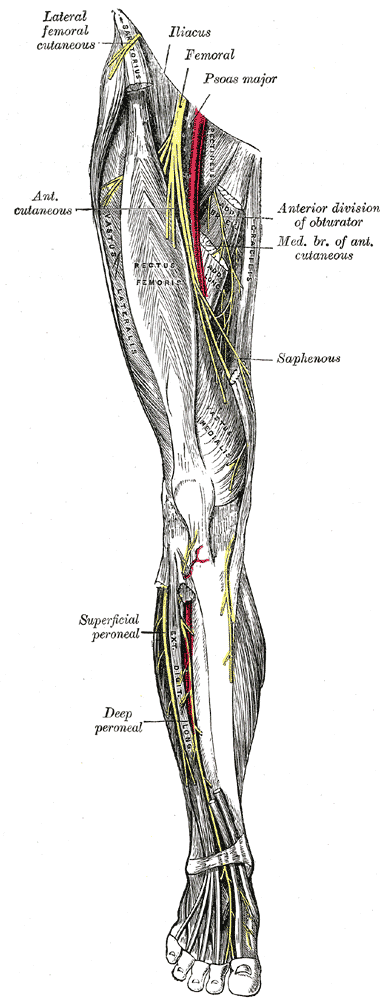
Anatomy
- Formed from the posterior divisions of L2 to L4
- Emerges at the lateral border of psoas and runs between psoas and iliacus
- Passes beneath the inguinal ligament lateral to the femoral artery
- Divides within the femoral triangle into anterior and posterior divisions
- Lies outside the femoral sheath
Motor Supply
- Iliacus and sartorius
- Pectineus in most people
- Quadriceps femoris
Sensory Supply
- Anterior thigh through the anterior cutaneous branches
- Medial leg and foot through the saphenous nerve
Clinical Features
- Weak knee extension with buckling and an absent knee reflex
- Numbness of the anterior thigh and medial leg
- Causes include iliacus haematoma from anticoagulation or haemophilia, retractors in hip arthroplasty and pelvic surgery, lithotomy positioning and femoral catheterisation
- Hip adduction is preserved, which separates a femoral neuropathy from an L3 or L4 radiculopathy
- Femoral nerve block causes temporary quadriceps weakness and a risk of falls
Investigations
- CT for iliacus haematoma
- EMG
Differential Diagnosis
- L3 or L4 radiculopathy
- Quadriceps tendon rupture
Management
- Most retractor neurapraxias recover
- Drain an expanding iliacus haematoma causing palsy
- Knee extension brace while recovering
Structures at Risk
- Anterior acetabular retractors placed over the anterior wall
- Anterior and anterolateral hip approaches
- Psoas retraction in lateral lumbar interbody fusion
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.