
Anatomy
- Formed from the anterior divisions of L2 to L4
- Descends along the medial border of psoas and the pelvic side wall
- Leaves the pelvis through the obturator canal with the obturator vessels
- Divides into anterior and posterior branches around adductor brevis
- An accessory obturator nerve is present in some people
Motor Supply
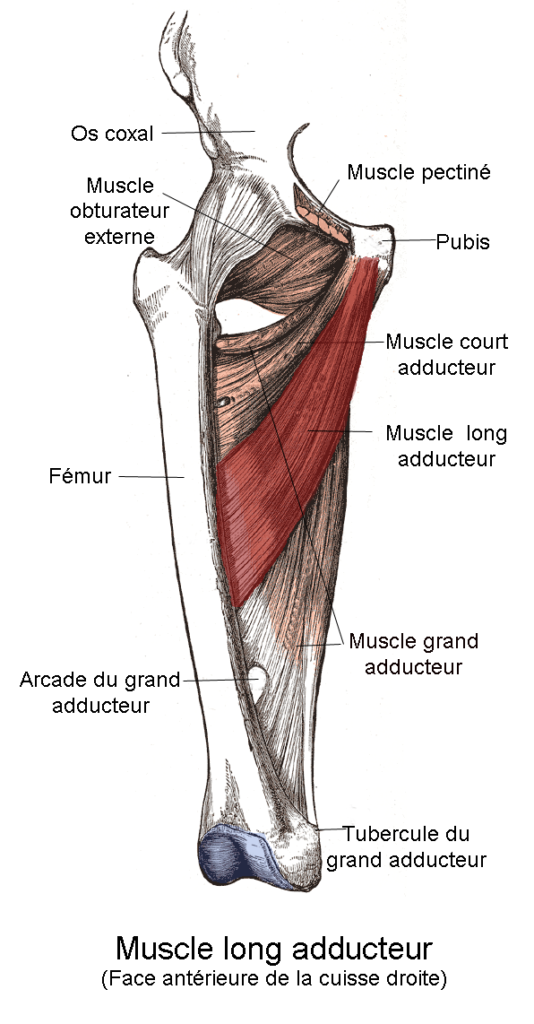
- Adductor longus, brevis and the adductor part of adductor magnus
- Gracilis and obturator externus
Sensory Supply
- Medial thigh
- Articular branches to the hip and knee, so hip disease can present as knee pain
Clinical Features
- Weak adduction with a wide based gait
- Medial thigh numbness
- Causes include pelvic and acetabular fractures, pelvic surgery and tumours, and medial screw or cement extrusion in hip arthroplasty
- Fascial entrapment in athletes causes exercise induced medial thigh pain
- Howship-Romberg sign is medial thigh pain from an obturator hernia
Investigations
- MRI of the pelvis
- EMG of the adductors
Differential Diagnosis
- Adductor strain
- L3 radiculopathy
- Hip osteoarthritis
Management
- Remove an offending screw or cement
- Fascial release for athletes
- Obturator neurectomy for adductor spasticity in cerebral palsy
Structures at Risk
- Acetabular screws in the anteroinferior quadrant
- Stoppa and ilioinguinal approaches
- Retractors placed beneath the transverse acetabular ligament
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.