
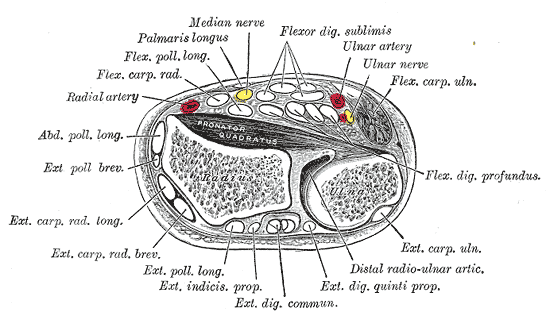
Anatomy
- Motor branch of the median nerve arising about 5 cm distal to the elbow joint
- Runs on the interosseous membrane between FPL and FDP
- Ends in pronator quadratus and sends sensory fibres to the wrist joint
- No cutaneous supply
Motor Supply
- Flexor pollicis longus
- FDP to the index and middle fingers
- Pronator quadratus
Clinical Features
- Unable to make an OK sign because thumb IP and index DIP flexion are lost
- Pinch becomes pulp to pulp with straight joints
- No sensory loss
- The nerve most often injured in extension type supracondylar humerus fractures with posterolateral displacement
- Other causes are forearm fractures, fibrous bands, an accessory head of FPL (Gantzer muscle) and neuralgic amyotrophy
- Test pronator quadratus with resisted pronation in full elbow flexion
Investigations
- EMG to confirm the lesion and exclude a partial median nerve injury
- MRI if neuritis or a mass is suspected
Differential Diagnosis
- Partial median nerve injury
- FPL tendon rupture in rheumatoid arthritis (Mannerfelt lesion)
Management
- Most fracture related and neuritic palsies recover, so observe for 3 to 6 months
- Exploration when there is no recovery
- Tendon transfers for permanent loss, such as brachioradialis to FPL and side to side FDP tenodesis
Structures at Risk
- Anterior approach to the proximal radius
- Reduction and pinning of supracondylar humerus fractures
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.