
Anatomy
- L4 to S2, the lateral division of the sciatic nerve
- Winds around the fibular neck through the fibular tunnel under peroneus longus
- Superficial peroneal nerve supplies the peronei and most of the dorsum of the foot
- Deep peroneal nerve supplies tibialis anterior, EHL, EDL, peroneus tertius, EDB and the first web space
- Vulnerable as superficial, tethered, with few large fascicles and a long course
Aetiology
- Knee dislocation, especially with posterolateral corner injury, varus traction stretching a long zone
- Biceps femoris avulsion and fibular head avulsion fractures
- Fibular neck and tibial plateau fractures
- Pressure from casts, bandages, theatre positioning, leg crossing, bed rest and rapid weight loss
- Iatrogenic in HTO, fixed valgus correction in knee arthroplasty, inside-out lateral meniscal repair and fixator pins
Clinical Features
- Foot drop with high stepping gait, weak dorsiflexion and eversion, dorsal foot sensory loss
- Inversion (tibialis posterior) and plantarflexion preserved
- L5 radiculopathy also weakens tibialis posterior and gluteus medius
Investigations
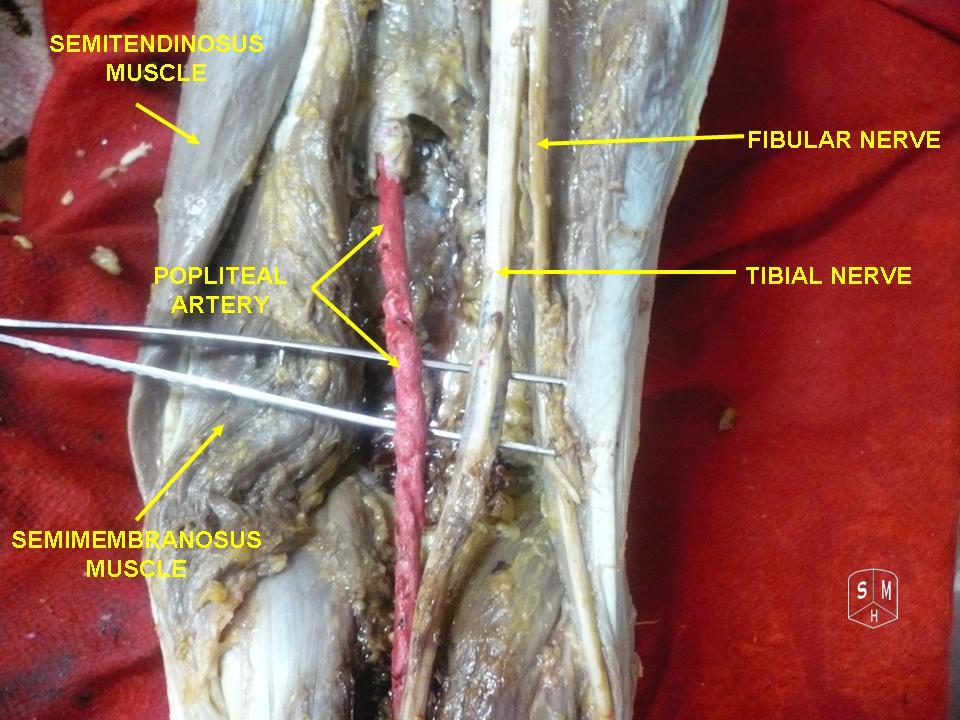
- NCS and EMG at 3 to 4 weeks, including short head of biceps to exclude a sciatic lesion
- MRI or ultrasound for ganglion, tumour or discontinuity
Management
- Remove external pressure, after knee arthroplasty loosen dressings and flex the knee
- AFO and daily calf stretching prevent equinus while awaiting recovery
- Open injuries explored, sharp lacerations repaired primarily
- Closed traction injuries observed, explored if no clinical or electrical recovery by about 3 months
- Neurolysis, grafting (poor with long grafts) or tibial branch transfer to the deep peroneal motor branch
- Intraneural ganglia decompressed with articular branch ligation to prevent recurrence
Tibialis posterior transfer
- Standard transfer for persistent foot drop, through the interosseous membrane to the lateral cuneiform
- Bridle procedure splits it to tibialis anterior and peroneal tendons
- Needs an intact tibial nerve, adequate tibialis posterior power and a supple ankle
- Most walk without an orthosis, with limited active dorsiflexion
Prognosis
- Poorer recovery than the tibial nerve
- Complete lesions after knee dislocation with a long zone often do not
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.