
Question
A 29 year old skier falls with a pole in her hand. She has pain and swelling on the ulnar side of the thumb MCP joint.
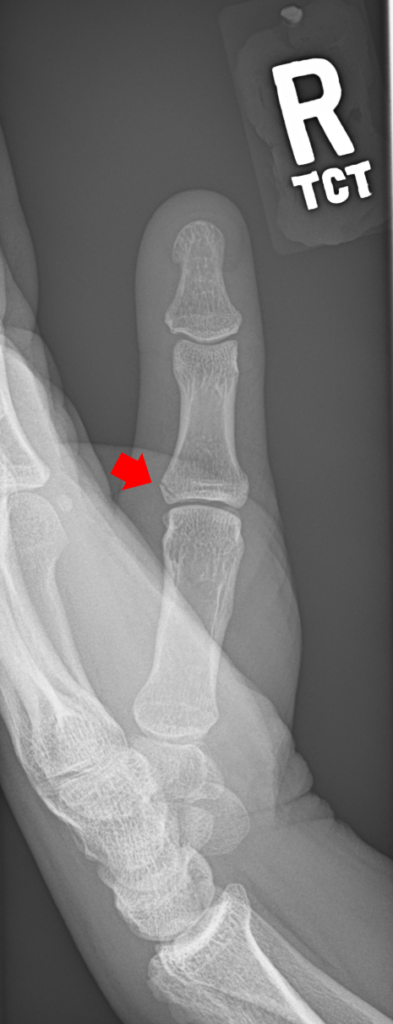
- What is the injury and how is it examined?
- What is a Stener lesion?
- Outline management.
Answer
Injury and examination
- Ulnar collateral ligament injury of the thumb MCP joint (skier’s thumb, gamekeeper’s thumb when chronic)
- Radiograph first to exclude a displaced avulsion fracture before stress testing
- Stress in 30 degrees of flexion tests the proper collateral
- Stress in full extension tests the accessory collateral and volar plate
- Laxity over 30 to 35 degrees or 15 degrees more than the other side, or no firm end point, means complete rupture
- Local anaesthetic helps if pain limits examination
Stener lesion
- Torn distal UCL displaced superficial to the adductor pollicis aponeurosis
- Aponeurosis blocks ligament healing
- Present in most complete ruptures
- Palpable lump proximal to the adductor aponeurosis
- Ultrasound or MRI if uncertain
Management
- Partial tears, hand based thumb spica for 4 to 6 weeks
- Complete tears and Stener lesions, early repair with a suture anchor into the base of the proximal phalanx
- Displaced or rotated avulsion fractures over 2 mm, fixation
- Chronic instability, free tendon graft reconstruction
- MCP fusion for arthritis
Related pages
Author Contributions
Orthofracs team
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.