
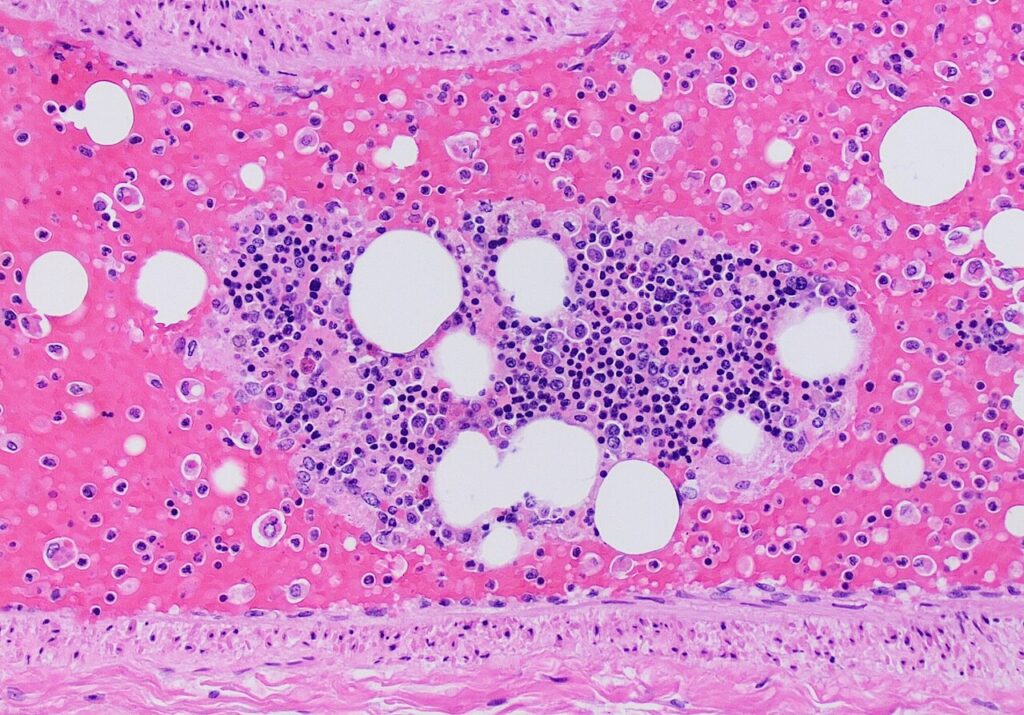
Fat Embolism Syndrome
- Follows long bone and pelvic fractures, onset 24 to 72 hours after injury
- Triad of hypoxia, confusion and petechial rash
- Petechiae in the axillae, conjunctivae and oral mucosa
- Diagnosis is clinical (Gurd criteria)
- Subclinical fat embolism is common after long bone fracture
- Mechanical and biochemical theories explain the syndrome
Gurd Criteria
| Major | Minor |
|---|---|
| Respiratory insufficiency | Tachycardia and fever |
| Cerebral involvement | Retinal fat emboli and jaundice |
| Petechial rash | Anaemia, thrombocytopenia, raised ESR and fat macroglobulinaemia |
- One major and four minor criteria with fat macroglobulinaemia
ARDS
- Berlin definition is onset within one week, bilateral opacities and hypoxia not explained by cardiac failure
- Severity by PaO2 to FiO2 ratio, mild 200 to 300, moderate 100 to 200, severe 100 or less
- Lung protective ventilation with low tidal volumes
- Prone positioning in severe cases
- Conservative fluid strategy
- Causes include sepsis, aspiration, massive transfusion and trauma
Management
- Supportive care with oxygen and ventilation
- Early stabilisation of long bone fractures lowers pulmonary complications (Bone, JBJS 1989)
- Damage control orthopaedics for borderline and unstable patients
- Reaming increases embolic load
- Avoid excessive reaming pressure and vent the canal
- Steroids are not routinely recommended
- Damage control orthopaedics in unstable patients
Related Pages
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.