
Question
A 52 year old builder has medial knee pain. Standing radiographs show isolated medial compartment osteoarthritis and 8 degrees of varus that corrects partly with valgus stress.
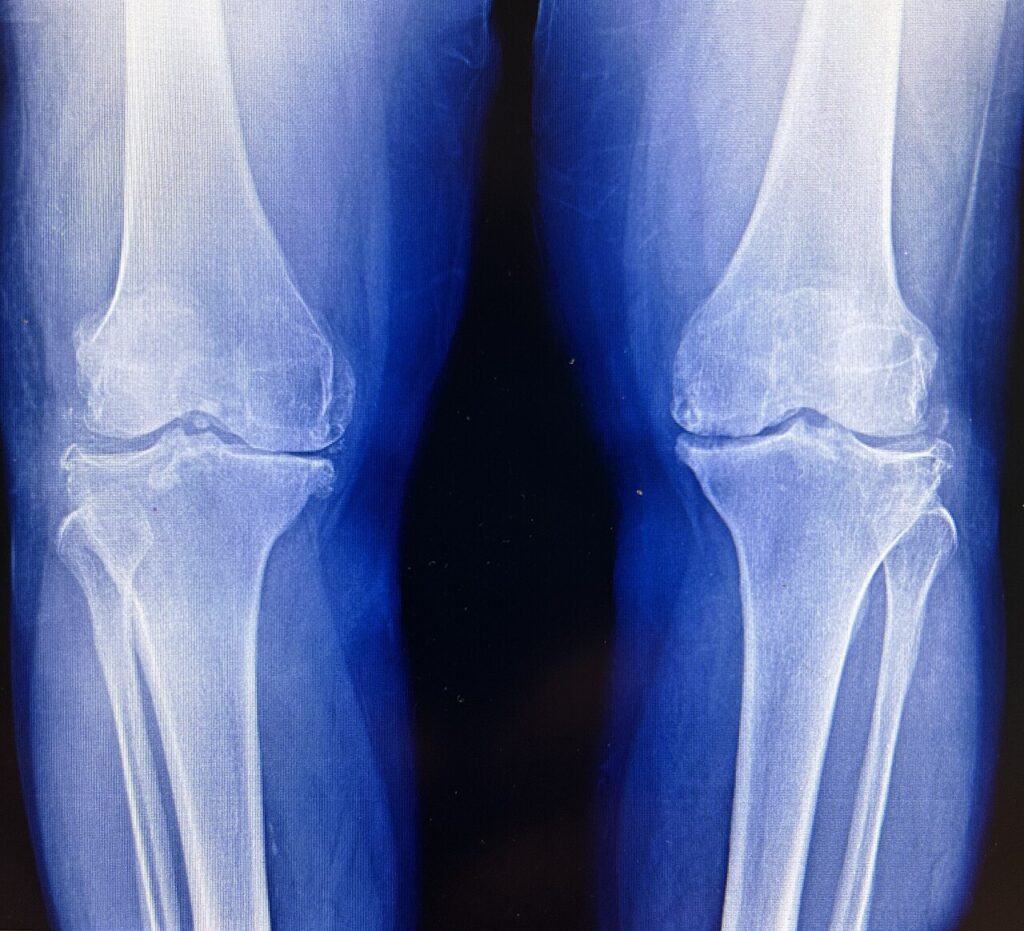
- What are the surgical options?
- What are the indications for high tibial osteotomy?
- How would you choose between osteotomy and unicompartmental arthroplasty?
Answer
Surgical options
- Medial opening wedge or lateral closing wedge high tibial osteotomy
- Unicompartmental knee arthroplasty
- Total knee arthroplasty
Indications for high tibial osteotomy
- Younger, active patients, typically under 55 to 60, and heavy manual workers
- Isolated medial compartment disease with a varus deformity from the tibia
- Range of motion at least 90 degrees with a flexion contracture under 15 degrees
- Stable ligaments, non-smoker and BMI under about 30
- Aim to shift the mechanical axis to just lateral of the midline (Fujisawa point, about 62% of tibial width)
Choosing between options
- Osteotomy suits younger patients with high activity demands and extra-articular deformity, preserving the joint
- Unicompartmental arthroplasty suits older, lower demand patients with anteromedial osteoarthritis, an intact ACL, a correctable deformity and full thickness lateral cartilage
- Unicompartmental arthroplasty gives faster recovery and better function than total knee arthroplasty but a higher revision rate in registry data (AOANJRR)
- Total knee arthroplasty for multicompartment disease or inflammatory arthritis
Related pages
Author Contributions
Orthofracs team
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.