
Question
A 30 year old motorcyclist has a grossly unstable knee after a high energy injury. The knee was reduced in the emergency department.
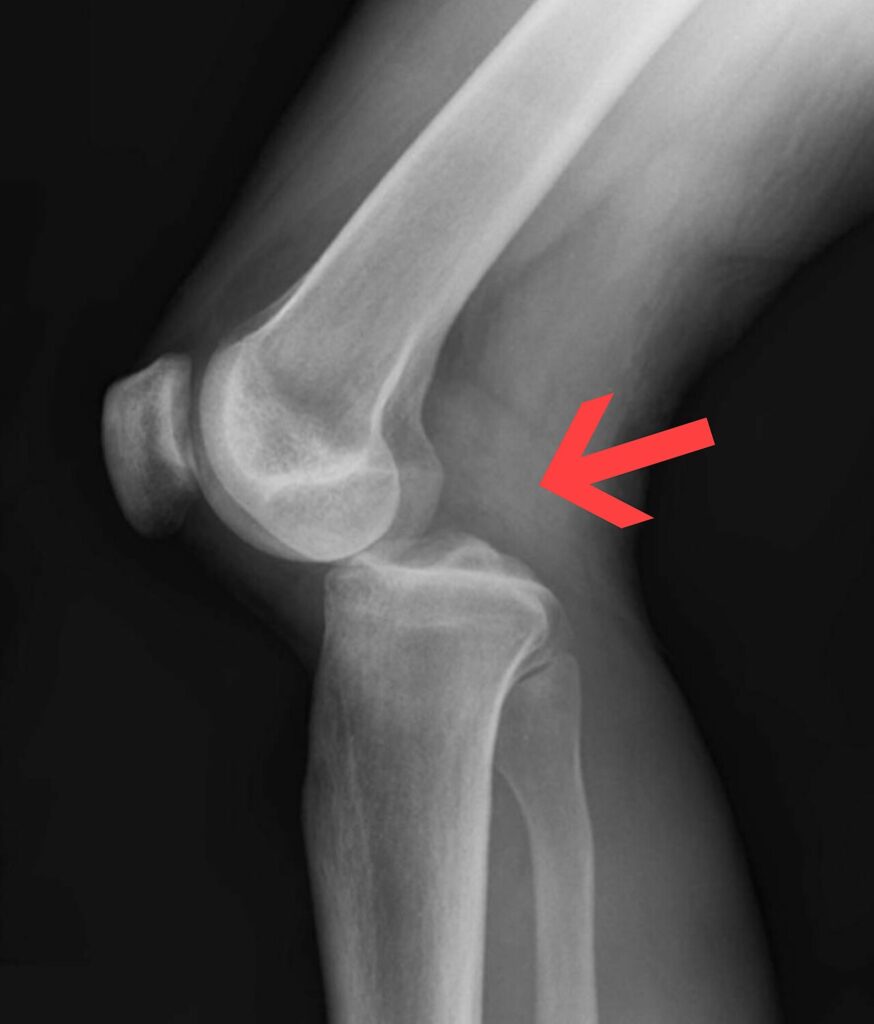
- What is the injury and how is it classified?
- What are the immediate priorities?
- Outline definitive management.
Answer
Injury and classification
- Knee dislocation with multiligament injury, which may have reduced spontaneously
- Schenck anatomical classification KD I to KD V by the ligaments torn, with KD V including fracture dislocation
- Direction of dislocation (Kennedy), anterior most common
Immediate priorities
- Vascular injury to the popliteal artery in up to a third
- Serial pulse examination and ankle brachial index, with CT angiography if the ABI is under 0.9 or pulses are abnormal
- Urgent vascular repair and fasciotomy for ischaemia
- Common peroneal nerve injury in up to 25%
- Splint or spanning external fixation, monitoring for compartment syndrome
Definitive management
- MRI to define all injured structures
- Early surgery within about 3 weeks for repair or reconstruction of the collateral ligaments and corners
- Reconstruction of ACL and PCL, often in one stage
- Posterolateral corner repair alone has a high failure rate, so reconstruction is preferred
- Rehabilitation focuses on motion, as stiffness is common
- Common peroneal nerve palsy may need tibialis posterior transfer if it does not recover
Related pages
Author Contributions
Orthofracs team
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.