
Indications
- Mainly arthroplasty, with a low dislocation rate
- Total hip replacement
- Hemiarthroplasty for femoral neck fracture
- Revision arthroplasty
Position
- Supine with the greater trochanter at the table edge so the buttock falls away
- Lateral decubitus as an alternative
Landmarks and Incision
- Palpate the greater trochanter and femoral shaft
- Straight longitudinal incision centred on the trochanter tip, in line with the femur
Internervous Plane
- No internervous plane
- Gluteus medius is split, and both medius and minimus are supplied by the superior gluteal nerve
- Vastus lateralis (femoral nerve) is also split
Superficial Dissection
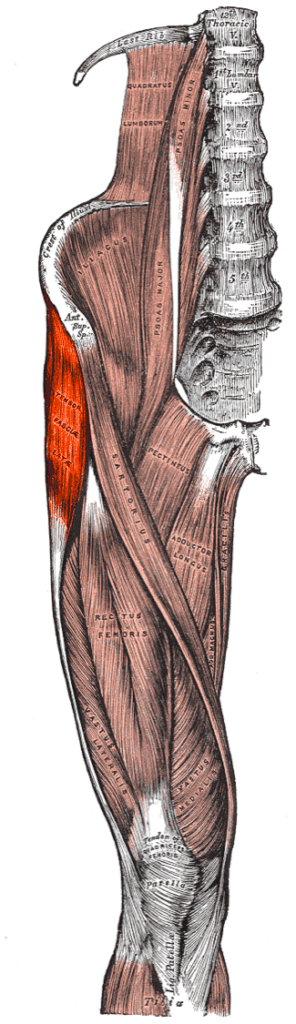
- Fascia lata incised between TFL anteriorly and gluteus maximus posteriorly
- Trochanteric bursa divided to expose the gluteus medius insertion and vastus lateralis origin
Deep Dissection
- Anterior third to half of gluteus medius elevated in continuity with anterior vastus lateralis
- Tendinous sleeve linking them over the anterior trochanter is preserved
- Medius split extends no more than about 5 cm above the trochanter tip
- This limit protects the superior gluteal nerve
- Gluteus minimus released from the anterior trochanter or taken with the medius flap
- Capsule incised and hip dislocated anteriorly with external rotation, flexion and adduction
- Secure repair of the abductor sleeve at closure
Structures at Risk
- Superior gluteal nerve between medius and minimus above the safe zone
- Superior gluteal nerve injury causes abductor weakness and Trendelenburg gait
- Femoral nerve, artery and vein from retractors over the anterior acetabular rim
- Abductor repair failure with persistent limp and lateral hip pain
- Heterotopic ossification, more common than with the posterior approach
Extension
- Distal extension splits vastus lateralis to expose the femoral shaft
- Proximal extension limited by the superior gluteal nerve
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.