
Question
A 42 year old man felt a kick to the back of his calf while playing squash. He cannot rise on tiptoe and there is a palpable gap above the heel.
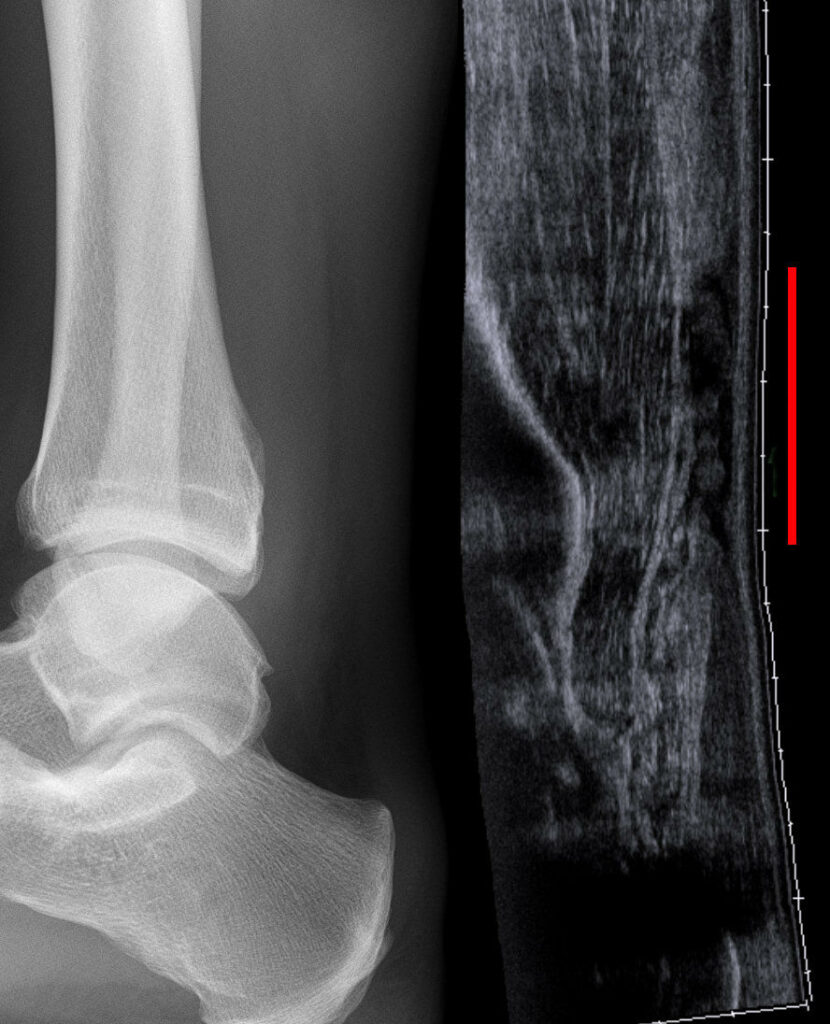
- How would you confirm the diagnosis?
- What are the treatment options and what does the evidence show?
- How would you manage a rupture that presents 3 months later?
Answer
Diagnosis
- Acute Achilles tendon rupture in the watershed zone 2 to 6 cm above the insertion
- Positive Simmonds (Thompson) calf squeeze test
- Loss of resting equinus with the patient prone and knees flexed (Matles test)
- Palpable gap
- Ultrasound for the gap and tendon end apposition in plantarflexion
Treatment and evidence
- Functional rehabilitation in an equinus boot with early weight bearing gives re-rupture rates similar to surgery (Willits, JBJS Am 2010, and UKSTAR, Lancet 2020)
- Surgery has lower re-rupture when rehabilitation is not accelerated, at the cost of wound complications and sural nerve injury
- Open or minimally invasive repair suits young athletes or patients with a gap in plantarflexion
- VTE prophylaxis is considered while immobilised
Chronic rupture
- Assess the gap on MRI
- Gap under 2 to 3 cm, end to end repair
- Gap 3 to 6 cm, V-Y advancement or turndown flap
- Gap over 6 cm, FHL transfer, often with V-Y or turndown
- Rehabilitation as for acute repair
Related pages
Author Contributions
Orthofracs team
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.