
Definition
- Prolapsed disc material may press on the dura resulting in neck pain & stiffness or the nerve root causing pain & paraesthesia in one or both arms
Aetiology
- Associated with
- heavy lifting
- smoking
Epidemiology
- MaleFemale 1.4:1
Anatomy
- Seven cervical vertebrae with eight cervical nerve roots
- Each root exits above its numbered pedicle, so C6 root exits at C5/6
- C8 root exits at C7/T1
- Roots run horizontally, so one disc compresses one root
- PLL is thickest centrally, so herniation is mostly posterolateral
- Uncovertebral joint hypertrophy narrows the foramen anteromedially
- Commonest levels are C5/6 then C6/7
Pathology
- Degenerate or traumatic tear of the annular fibres allowing prolapse of the intervertebral disc material
Classification
| Basis | Types |
|---|---|
| Location | Central, posterolateral or foraminal |
| Morphology | Protrusion, extrusion or sequestration |
- Central herniation compresses the cord and causes myelopathy
- Posterolateral and foraminal herniation compress the exiting root and cause radiculopathy
- Soft disc herniation contrasted with hard disc from a spondylotic osteophyte bar
History
- Pain
- Onset usually not related to severe strain & often occurs on stretching upon waking
- often radiates to the scapular region & sometimes the occiput
- Radicular pain (brachialgia) to one (rarely both) arms in the distribution of innervation of involved segment
Nerve roots in order of effect = C7, C6, C5, C8
- C7 – Triceps
- Dorsal forearm pain
- Medial scapular pain
- Tip of index finger numbness
- Absent triceps jerk
- C6 – Biceps compartment pain
- Biceps weakness
- Tip of thumb ↓ sensation
- Depressed biceps jerk
- C5
- Short history because of noticeable reduction in shoulder abduction
- Severe effects
- Obvious signs & disability
- C8 – Scapular pain
- Medial brachial / axillary radiation
- Severe impact on hand function
- Similar to an ulnar nerve lesion
Examination
- Look
- Torticollis – neck may be tilted
- Palpation
- tender spots are palpated in the cervical musculature (trapezius & scapular region)
- Movements
- Some movements are restricted & painful but at least one movement is full & painless in all but the most severe cases
- May be weakness of muscle groups innervated by the affected root
- Special tests
- Foraminal compression test
- often positive & abduction / external rotation of the arm without changing neck position relieves the pain (hand behind the head)
- Foraminal compression test
- Note
- commonest level is above or below the sixth cervical vertebra involving the C6 or C7 roots
- Upper limb movements are full
- commonest level is above or below the sixth cervical vertebra involving the C6 or C7 roots
Investigations
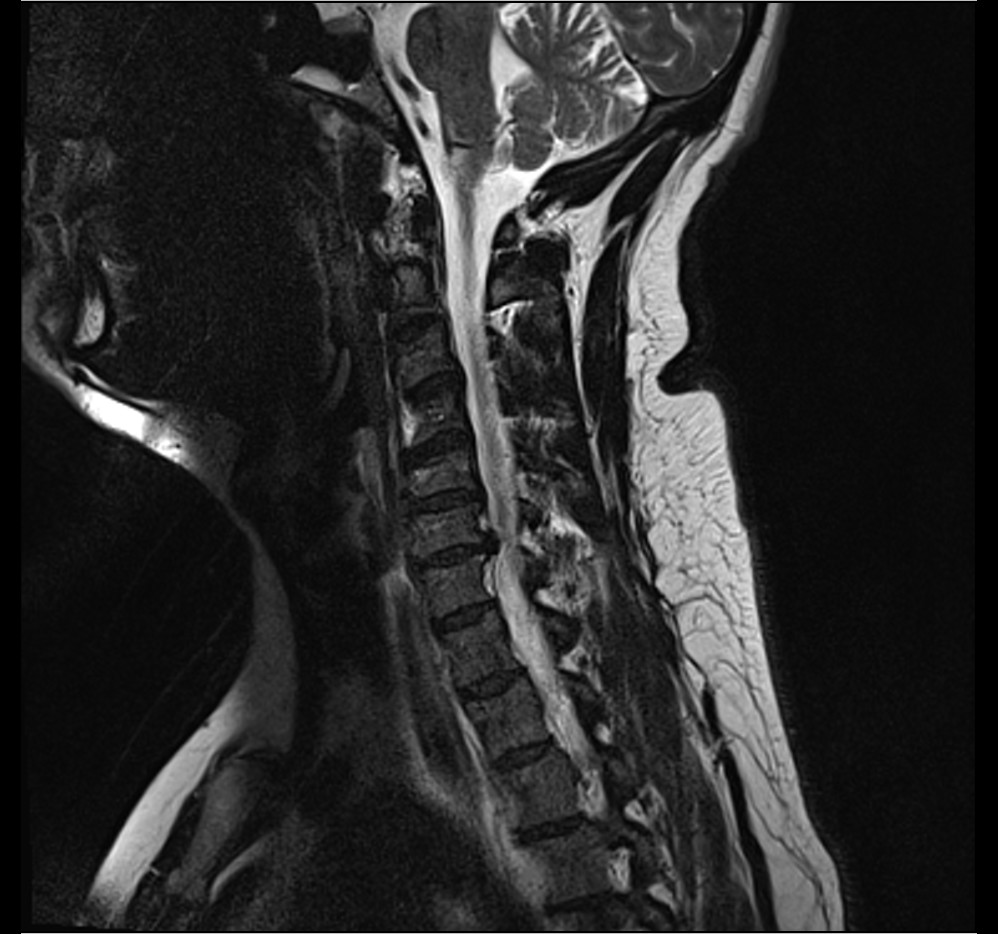
- X-ray
- Loss of normal cervical lordosis
- Disc space is often narrowed
- CT
- gives variable image quality
- Myelography
- rarely used now
- MRI
- gold standard
Differential Diagnosis
- Cervical rib syndrome involving C8/T1 roots
- Carpal tunnel syndrome where neck movements are painless
- Supraspinatus tendon lesions or other shoulder pathology
- Tumours of the cervical spine or region may present with radicular symptoms
- Cervical spine infection
- Neuralgic Amyotrophy where pain is sudden & severe with multiple levels involved
Treatment
- Nonoperative
- Rest, analgesics & anti-inflammatories (80 – 90% resolve!)
- Occasional role for oral steroids
- A soft cervical collar may be useful in the short term to improve comfort
- Cervical traction
- may also provide relief of symptoms & provide comfort while the condition resolves (should not exceed 10lbs which is the approximate weight of the head)
- Operative
- Decompression
- If symptoms severe & refractory operative decompression may be indicated
- anterior approach with subsequent stabilisation of the cervical spine
- bone graft ± internal fixation
- foraminectomy ± discectomy
- Decompression
Complications
Disease
- Persistent motor deficit from prolonged root compression
- Myelopathy from central herniation
Surgery
- Dysphagia after ACDF, mostly transient
- Recurrent laryngeal nerve palsy with hoarseness
- Pseudarthrosis, higher with multilevel fusion
- Adjacent segment disease at about 3% per year after ACDF
- C5 palsy after decompression
Prognosis
- Most cervical radiculopathy improves with non-operative care over weeks to months
- Sequestrated fragments often regress on serial MRI
- ACDF relieves arm pain in most patients
- Arm pain responds better to surgery than neck pain
- Established motor deficit recovers less predictably than pain
- Myelopathy from disc herniation does better with early decompression
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.