
Overview
- Second generation resurfacing and large head THR aimed to cut wear and dislocation in young patients
- AOANJRR and other registries showed high revision rates for several designs
- Wear debris causes ARMD, pseudotumour, soft tissue necrosis and raised cobalt and chromium
- Risks are small components, female sex and steep cup inclination
- Regular review with symptoms, blood metal ions and MARS MRI or ultrasound
Western Health Orthopaedic Registrar presentation – Modern Metal on Metal Implants in Hip Surgery by Dr Darren Webb
Epidemiology
- Large head metal on metal and resurfacing were popular in the 2000s
- The AOANJRR and other registries identified high revision rates
- DePuy ASR and ASR XL were recalled in 2010, with very high ASR XL failure
- Better performing resurfacing designs continue in selected men with large heads
Pathology
- ARMD covers metallosis, pseudotumour, ALVAL (type IV hypersensitivity), osteolysis and abductor destruction
- Risks are steep or malverted cups, reduced coverage arc, small components, female sex and dysplasia
- Cobalt toxicity is rare, causing cardiomyopathy, hypothyroidism, neuropathy, visual or hearing loss
- Renal impairment contraindicates these bearings
Investigations
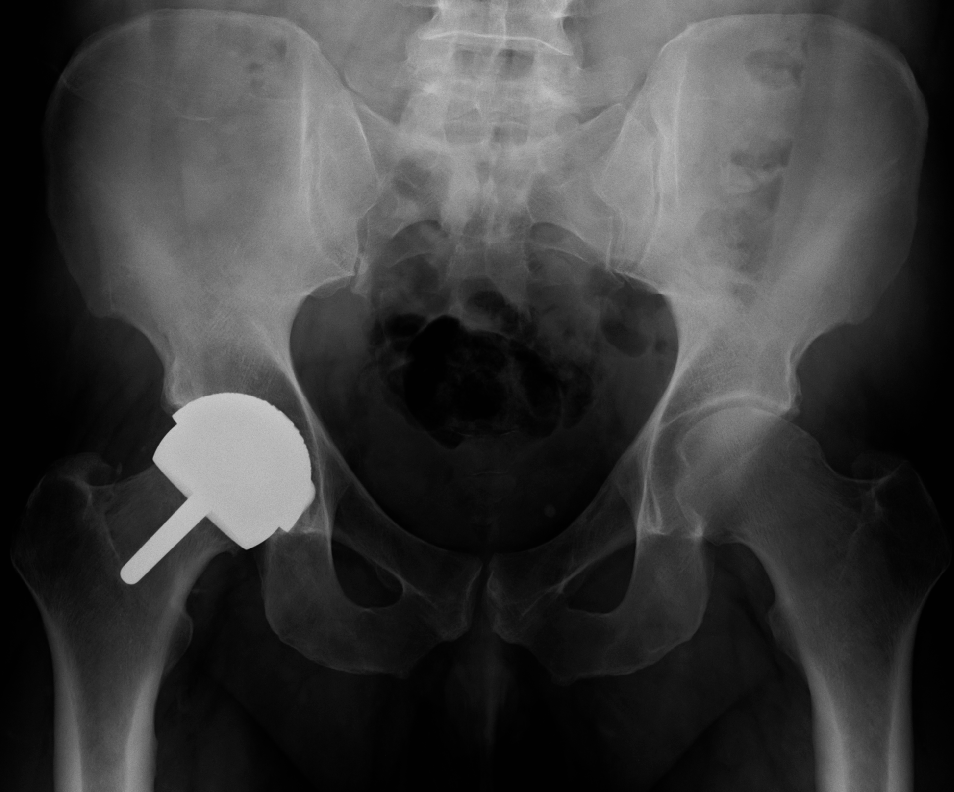
- Whole blood cobalt and chromium, with concern above about 7 micrograms per litre
- Rising serial levels are more significant than one value
- MARS MRI or ultrasound for soft tissue lesions
- Annual review of high risk patients with scores, radiographs, ions and cross-sectional imaging
Management
- Revise early before abductor destruction, as pseudotumour revision outcomes are worse
- Debride while protecting the sciatic and femoral nerves
- Change to ceramic on polyethylene
- Retain a well fixed modular cup with liner exchange, and remove monoblock cups
- Titanium sleeved ceramic head on a retained taper
- Dual mobility or larger heads if instability risk is high
- Follow ions until normal
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.