
Definition
- Abnormal development of the hip ranging from acetabular dysplasia to subluxation and dislocation
- Terms defined in Developmental Dysplasia of the Hip Definitions
Aetiology
- Risk factors are breech presentation, family history, female sex and first born
- Oligohydramnios and other packaging problems
- Associated with torticollis and metatarsus adductus
- Left hip more often affected
Clinical Features
- Ortolani test reduces a dislocated hip
- Barlow test dislocates a reducible hip
- Both become unreliable after about 3 months as soft tissues tighten
- Later signs are limited abduction, Galeazzi sign and asymmetric skin creases
- Walking child shows a Trendelenburg gait and leg length difference
Investigations
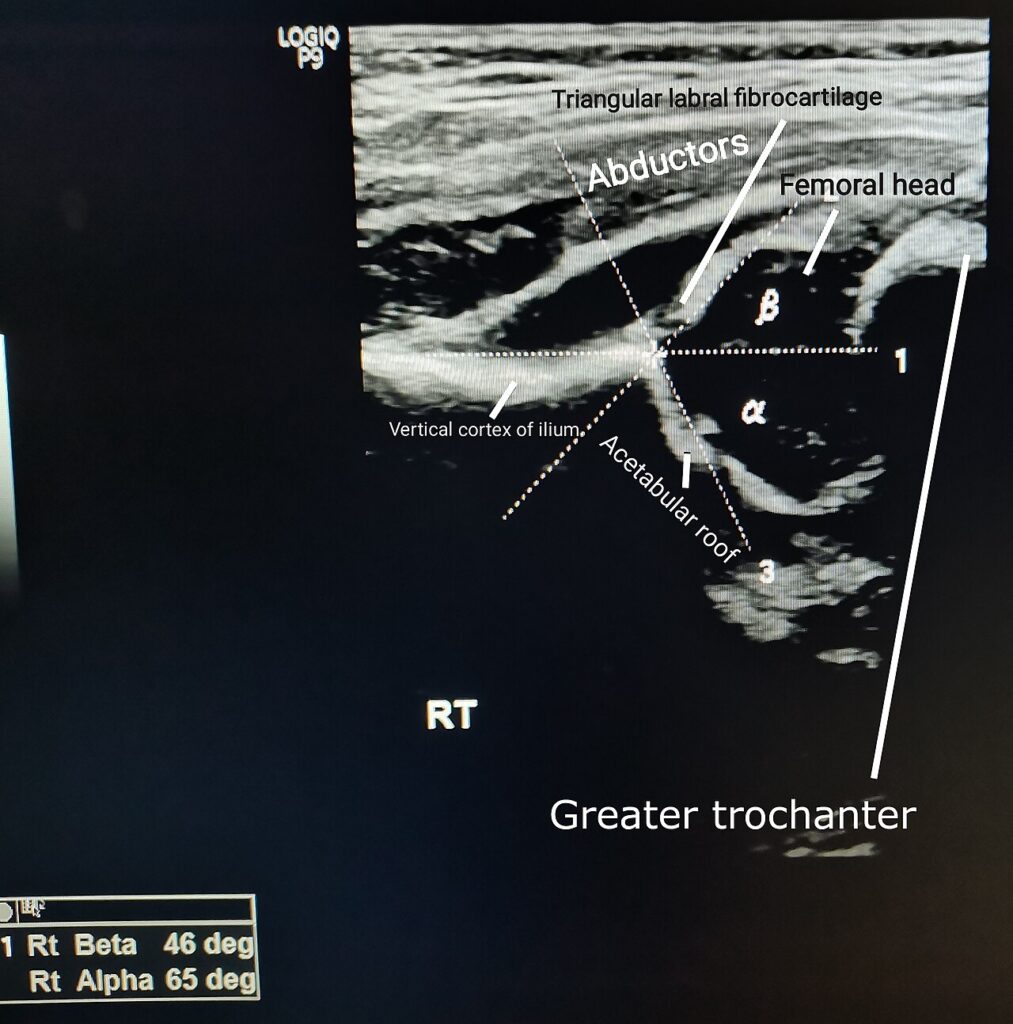
- Ultrasound before 4 to 6 months, using the Graf method
- Graf alpha angle of 60 degrees or more is normal
- X-ray after 4 to 6 months once the femoral head ossifies
- Assess Hilgenreiner and Perkin lines, acetabular index and Shenton line
Management
| Age | Treatment |
|---|---|
| Under 6 months | Pavlik harness with hips flexed to about 100 degrees and abducted within the safe zone. Weekly review with ultrasound. Abandon if not reduced by 3 weeks |
| 6 to 18 months | Closed reduction under anaesthesia with arthrogram, adductor tenotomy and hip spica in the human position for about 12 weeks |
| Over 18 months | Open reduction, often with femoral shortening and a pelvic osteotomy |
- Human position is about 100 degrees flexion with abduction inside the Ramsey safe zone
- Excess abduction risks avascular necrosis
Complications
- Avascular necrosis of the femoral head
- Femoral nerve palsy from excess flexion in the harness
- Pavlik disease, posterior acetabular wall erosion from persistent dislocation in the harness
- Residual dysplasia and redislocation
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.