
Definition
- Historical name for acute disseminated multisystem LCH
- Most often under 2 years of age
- Most severe end of the LCH spectrum
Pathology
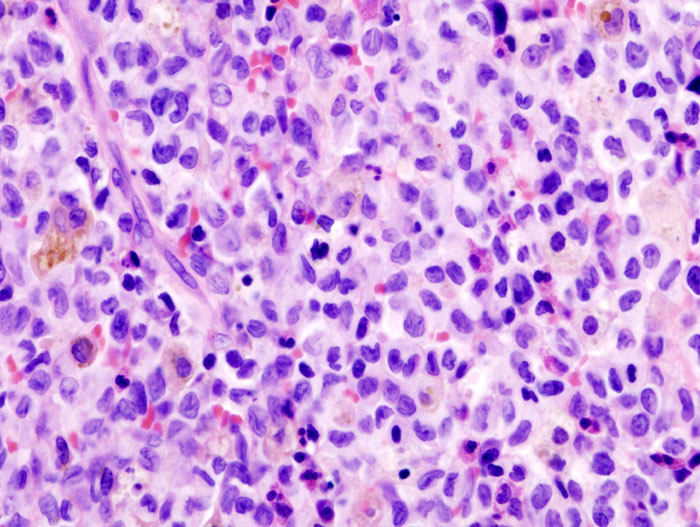
- Clonal Langerhans-type cells with grooved coffee bean nuclei
- Mixed eosinophils, lymphocytes and macrophages
- CD1a, langerin (CD207) and S100 positive
- Tennis racket Birbeck granules on electron microscopy
- MAPK pathway mutations, most often BRAF V600E, place LCH among myeloid neoplasms
Clinical Features
- Fever, failure to thrive and irritability
- Seborrhoeic rash of scalp, trunk and skin creases, sometimes purpuric
- Hepatosplenomegaly and lymphadenopathy
- Pancytopenia from marrow infiltration, with bleeding and infection
- Otitis media and otorrhoea
- Pulmonary involvement
- Multiple lytic bone lesions, particularly of the skull
Investigations
- FBC, liver function, coagulation and albumin
- Skeletal survey, whole body MRI or PET
- Bone lesions are punched out lytic defects without a sclerotic rim
- Chest and abdominal imaging for lung, liver and spleen
- Marrow examination when cytopenias are present
- Biopsy the most accessible lesion, often skin or bone
Classification
- Histiocyte Society system stratifies by disease extent
- Multisystem LCH with risk organ involvement (liver, spleen, haematopoietic system) is high risk
- This high risk group corresponds to Letterer-Siwe disease
Differential Diagnosis
- Leukaemia and metastatic neuroblastoma
- Haemophagocytic lymphohistiocytosis
- Congenital infection
- Non-accidental injury with multiple skeletal lesions
Management
- Vinblastine and prednisolone first line under paediatric oncology
- Cytarabine or cladribine for refractory disease
- BRAF and MEK inhibitors for refractory high risk disease
- Transfusion and infection management
- Orthopaedic role is biopsy and spinal or long bone lesions at fracture risk
Prognosis
- Depends on risk organ involvement and early treatment response
- Poor responders with risk organ dysfunction have substantial mortality
- Late effects include diabetes insipidus, orthopaedic deformity and neurodegenerative disease
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.