
Anatomy
- Positions the hand in space
- Acts as the forearm lever
- Weight bearing joint when using walking aids
- Three articulations, ulnohumeral, radiocapitellar and proximal radioulnar
- Carrying angle is valgus in extension
- Functional range 30 to 130 degrees flexion, 50 pronation and 50 supination (Morrey)
- Ulnohumeral joint highly congruent, stabilised by anterior bundle of MCL and LUCL
Aetiology
- Primary OA mainly in men with heavy manual work or weightlifting
- Inflammatory arthritis, mostly RA, also psoriatic arthritis and gout
- Post traumatic after intra articular fracture or instability
- Haemophilia, septic and neuropathic arthritis
Pathology
- Primary OA forms osteophytes on coronoid, olecranon and their fossae
- Joint space preserved until late in primary OA
- Loose bodies common in primary OA
- RA causes synovitis, concentric joint space loss, bone erosion and instability
Classification
Mayo (rheumatoid elbow)
| Grade | Description |
|---|---|
| I | Synovitis with normal radiographs |
| II | Joint space narrowing with preserved architecture |
| III | Altered architecture |
| IV | Gross destruction |
Clinical Features
- Primary OA gives end range pain from impingement, mid arc pain free
- RA gives pain through the arc with swelling and instability
- Locking from loose bodies
- Ulnar nerve symptoms common, examine the cubital tunnel
Investigations
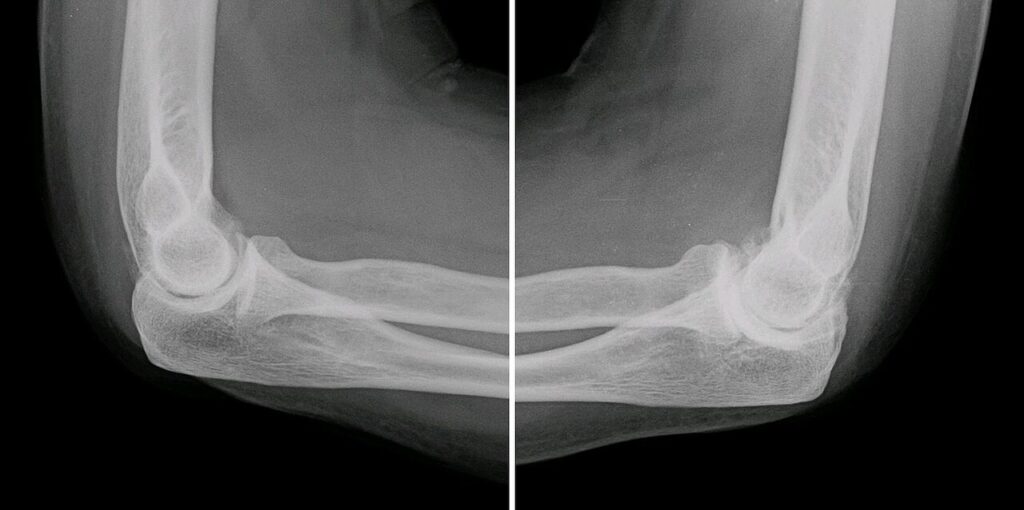
- AP and lateral radiographs
- CT with 3D reconstruction maps osteophytes and loose bodies
Management
- Activity modification, analgesia, NSAIDs and steroid injection
- Arthroscopic debridement for primary OA with impingement
- Open ulnohumeral arthroplasty (Outerbridge Kashiwagi) for primary OA
- Lateral column procedure for stiffness
- Ulnar nerve decompression or transposition with ulnar symptoms or marked flexion loss
- Synovectomy with or without radial head excision in early RA
- Interposition arthroplasty in young active patients
- Linked semiconstrained TEA (Coonrad Morrey) for RA and older low demand patients
- Lifting limit after TEA about 5 kg single and 1 kg repetitive
- Arthrodesis as salvage
Complications
- TEA infection, aseptic loosening and polyethylene wear
- Ulnar neuropathy, triceps insufficiency and periprosthetic fracture
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.