
Chondrosarcoma is a malignant cartilage forming tumour of adults, most often in the pelvis, proximal femur and proximal humerus. It resists chemotherapy and radiotherapy, so wide surgical excision is the main treatment, and histological grade guides prognosis.
Definition
- Malignant tumour of cartilage-producing cells
- Proximal femur
- Pelvic Girdle
- Knee
- Spine
- 20% of primary bone tumours
- 2nd in frequency to Osteosarcoma
- It has a wide range of biologic behaviour
- Low grade (grade 1): <5% risk of metastasis
- Intermediate grade (grade 2): 20-30% risk of metastasis
- Dedifferentiated (grades 3 and 4): 70% risk of metastasis
- Mesenchymal: >50% risk of metastasis
- 6-8th Decade of Life
Classification
- Classified according to
- Histological grade & subtypes
- Primary & Secondary
- Central & Peripheral
(1) Histological Grade & Subtypes
- Based on the histological appearance
- Conventional chondrosarcoma
- Hyaline or myxoid cartilage tumour of various grades
- Special types
- Clear cell
- Mesenchymal
- Soft tissue chondrosarcoma
- Chondrosarcoma of skull base
- De-differentiated
- Conventional chondrosarcoma
Conventional Chondrosarcoma
| Grade | Descriptions |
|---|---|
| 1 Low Grade | Resembles normal cartilage cells with mild cellular atypia Least risk of metastasis Frequent calcification |
| 2 Medium Grade | Frequent double nuclei Atypia with plump cells Rare multinucleated giant cells Calcification |
| 3 High Grade | Most abnormal-appearing cartilage with highest risk of metastasis Marked atypia & mitotic figures Double nuclei & crowding of lacunae Frequent multinucleated giant cells No calcification |
- lesions in axial skeleton & proximal appendicular skeleton more likely to be malignant than distal limb lesions (ie. the digits)
- Most chondrosarcomas are grade 1 or 2
- Chondrosarcomas are occasionally grade 3
- The only tumour that has higher risk of metastasizing than Grade 3 is De-differentiated Chondrosarcoma
Clear Cell Chondrosarcoma
- Young adults 20-50 years
- M:F – 2:1
- Low grade usually
- Thought to be malignant counterpart of the benign chondrhttp://chondroblastomaoblastoma
- Hence “epiphyseal chondrosarcoma”
- Most common in
- Proximal humerus
- Proximal femur
- Involve the epiphyseal centre & metaphysis
- Histology
- Larger & more rounded tumour cells with clear or vacuolated cytoplasm (sheets of clear cells)
- Abundant intracellular glycogen
- Chondroid & osseous matrix with numerous osteoclast-like giant cells (may resemble renal cell carcinoma)
- Foci of calcification
Mesenchymal Chondrosarcoma
- 2nd-3rd decade of life
- High-grade
- Less common than clear cell
- Most common in
- Rib
- Spine
- Pelvis
- Femur
- Can appear in soft tissues
- Histology
- Nodules of benign cartilage in background of undifferentiated small round cells (biphasic appearance)
- Small cell component has appearance of Haemangiopericytoma or Ewings
- 60% 5 year survival
Soft Tissue Chondrosarcoma
- Rare tumour
- Little about natural history
- Treated like other STS
Base of Skull Chondrosarcoma
- Confused with chondroma of clivus
- Presents with neurological deficits
- Treated with curettage & irradiation
De-differentiated Chondrosarcoma
- High-grade
- Non-chondroid sarcoma
- 10% of all chondrosarcomas
- Usually arises from
- Benign cartilage lesion
- Low grade chondrosarcoma
- Consists of areas of malignant spindle cells that cannot be recognised of cartilage origin adjacent to areas of neoplastic chondrocytes surrounded by hyaline ± bizarre giant cells
- Cartilage matrix has tissue resembling
- Osteosarcoma
- Fibrosarcoma
- MFH
- Most malignant of chondrosarcoma & highest rate of metastasis
(2) Primary & Secondary Types
| Type | Description |
|---|---|
| Primary | Arise de novo, most |
| Secondary, from pre-existing cartilage lesions | Osteocartilaginous exostosis Enchondroma (Ollier disease, Maffucci syndrome) Periosteal chondroma Chondroblastoma Chondromyxofibroma Synovial chondromatosis Earlier age of presentation than the primary tumours |
| Secondary, from other cause | Pagets Radiation Later presentation than the primary tumours |
(3) Central & Peripheral
Central (Medullary)
- Arise from
- medullary canal
- Meta-diaphyseal
- Metaphysis extending into diaphysis
- Femur & Humerus most commonly
- Meta-diaphyseal
- medullary canal
- All primary types are central
- Secondary types usually arise from Enchondroma
Peripheral (Juxtacortical)
- Arise from the surface of bone
- Pelvic & Shoulder girdle
- Upper Femur & Humerus
- Ribs
- Majority secondary to Exostosis
Risk of Malignant Transformation
- Solitary osteochondroma < 1%
- Diaphyseal aclasia 1% per year
- Solitary enchondroma < 1%
- Multiple enchondroma (Ollier’s*, Marfucci’s) 20-30%
- Patients with Ollier’s disease have 25% incidence of chondrosarcoma in lifetime
- Patients with Maffucci syndrome have 100% incidence of chondrosarcoma in lifetime
- Synovial chondromatosis 5%
Clinical Features
- Classically patients in 5th-6th decades
- 4% < 20yo
- M:F – 1.5:1
- Long history of pain & mass
- Most commonly seen in medullary cavity of
- Femur
- Humerus
- Pelvis (incl. acetabulum)
- Ribs
- Patients initially complain of mild local pain & swelling
- Laboratory findings normal
Radiography
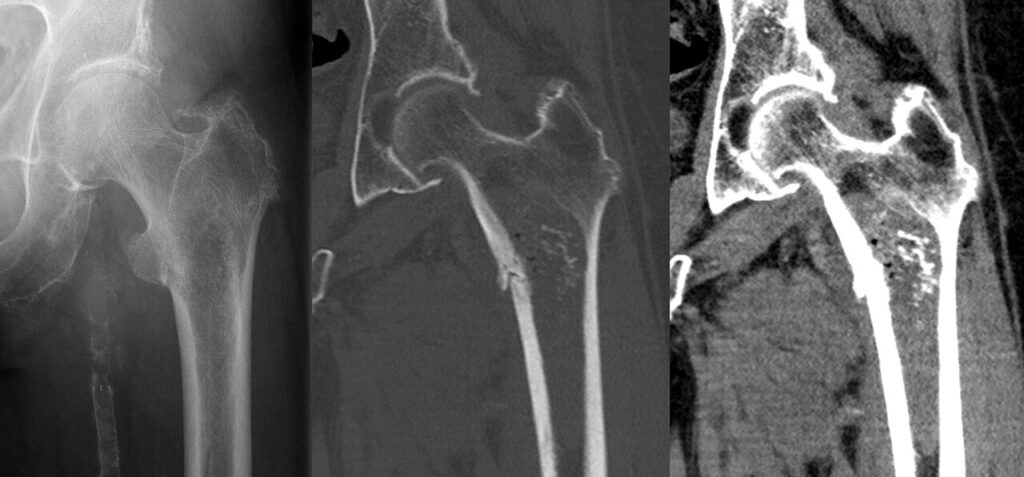
Central
- Diaphyseal or less often Metaphyseal
- Lucent expansile lesion
- Sclerotic margins
- Endosteal scalloping
- Intralesional calcification
- Amorphous
- Punctate
- Chicken Wire
- Popcorn
- Cortical destruction & soft tissue mass may be present
- More destructive lesions have
- Less calcification
- More scalloping
- More cortical destruction
Peripheral
- Soft tissue mass
- Multiple calcific densities
- Ill-defined margins
- Destruction of underlying bone
- Some are using Thallium & DMSA scans to differentiate low from high grade lesions
- uptake suggests ↑ metabolic activity (ie. high grade lesion)
- Approach to CLUMP lesions
- Bone scan cold
- expect good histological characteristics
- no need to biopsy
- Bone scan hot
- may have worrying histological features
- MRI with gadolinium producing a contrast enhancement curve with images taken at a specific site every 7 seconds for 2 minutes
- if there is a steep curve (rapid take-off) then suggestive of angiogenesis which may indicate aggressive lesion
- if so then should consider biopsy
- Bone scan cold
Histology
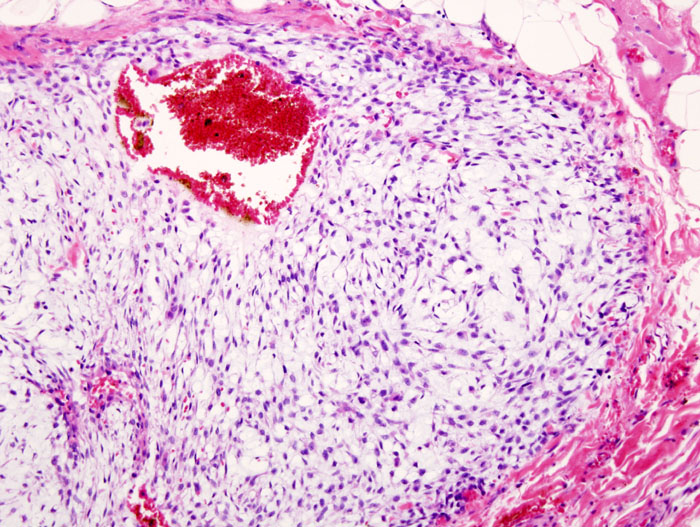
Gross
- Pearly white
- Cauliflower-like mass
- Surrounded by pseudocapsule
Histology
- Lobules of cartilage
- Matrix may have
- Calcification
- Necrosis
- Myxoid degeneration
- Features that suggest malignancy
- Pleomorphism
- Hypercellularity
- Mitotic figures
- Double nuclei in single lacunae
- Multinucleated Giant Cells
- Realise that the pathologist will accept chondromas with atypical features (↑ cellularity, binucleate cells, anaplasia etc) for certain lesions & still call them benign
- Solitary enchondroma
- Olliers or Marfucci’s
- Periosteal chondroma
- Synovial chondromatosis
- Some chondromas are indistinguishable from low grade chondrosarcoma
- 50% of Grade I chondrosarcomas are indistinguishable from cellular enchondroma
- Distinction is made on the radiological appearance (bone destruction etc), soft tissue extension, location etc
- Enchondromas & periosteal chondromas should be reviewed every year to see if they progress or change (particularly if multiple or part of a syndrome)
Genetics
- Numerous chromosomes have been implicated
- Patients with hereditary multiple exostoses and an EXT1 mutation are at higher risk than are patients with an EXT2 or EXT3 mutation
- Myxoid chondrosarcoma is associated with a 9-22 chromosomal translocation
Grading
- Grading based on complete patient
- Age
- Location
- XR
- Histology (see above)
- More likely to be worrisome if
- Central
- Large
- Old patient
- Polyploid
Differential Diagnosis
- Other cartilage tumours
- Chondrosarcomatous osteosarcoma
Treatment
- The mainstay of treatment is wide surgical resection
- Highly resistant to chemotherapy & radiotherapy
- Rate of DNA synthesis slow
- Slow growing, low grade nature of tumours
- Surgery should aim to be curative but sometimes margins are close d/t location of neurovascular structures
- Aggressive excision with wide margin
- Probably safest regardless of grade
- Adjunctive treatment rarely used
- May be indicated in
- High grade lesions
- Incomplete margins
- Phenol to lyse remaining tumour cells then neutralised with alcohol
- Irradiation most useful where wide resection not possible (eg. spine)
- High dose irradiation can arrest growth of the tumour for several years but will only delay the local recurrence
- Chemotherapy has been limited to the young patient with de-differentiated chondrosarcoma
- Little data to support usage & in metastatic disease will slow growth but cure rare
Prognosis
- Low-Moderate Grade
- If treated with wide excision
- 90% 5-year survival
- High Grade
- < 10% 5-year survival
- Thus patients with low grade tumours can expect a cure but metastasis common in high grade
- Depends on
- Histological grade
- Adequacy of resection
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.