
Overview
- Avulsion of the ACL insertion, the paediatric equivalent of an ACL tear
- Children aged 8 to 14, after a bike fall or sport
- Meyers and McKeever types I to III by displacement, IV comminuted
- Type I in an extension cast
- Medial meniscus anterior horn or intermeniscal ligament can block type II reduction
- Displaced fractures need arthroscopic or open fixation with sutures or screws
- Arthrofibrosis is a common complication
Western Health Orthopaedic Registrar presentation – Paediatric Tibial Eminence Fractures by Dr Amy Gibbens
Pathology
- The incompletely ossified epiphysis fails before the ACL
- Anterior horn of medial meniscus or intermeniscal ligament can become trapped beneath the fragment
- Peak age 8 to 14 years, commonly from a bicycle fall
Classification
Meyers and McKeever, Zaricznyj modification
| Type | Description |
|---|---|
| I | Minimally displaced |
| II | Anterior elevation with a posterior hinge, a beak on the lateral film |
| IIIA | Complete separation of the ACL insertion only |
| IIIB | Complete separation of the entire eminence |
| IV | Comminuted (Zaricznyj) |
Original publication Meyers MH, McKeever FM. Fracture of the intercondylar eminence of the tibia. J Bone Joint Surg Am. 1959;41-A(2):209-20; discussion 220-2.
Original publication Zaricznyj B. Avulsion fracture of the tibial eminence: treatment by open reduction and pinning. J Bone Joint Surg Am. 1977;59(8):1111-4.
Investigations
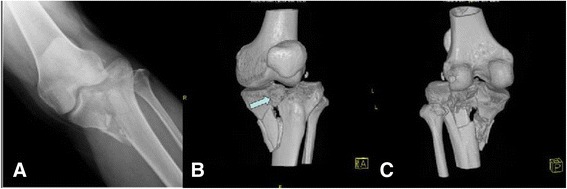
- Lateral radiograph shows displacement best
- MRI identifies entrapped meniscus and separates type II from III
Management
- Type I in a cast or brace for four to six weeks, avoiding hyperextension
- Type II reduced closed in extension after haemarthrosis aspiration
- Failed closed reduction suggests soft tissue entrapment
- Type III and IV need arthroscopic reduction and fixation
- Recess the fragment slightly to reduce residual laxity
- Sutures avoid hardware removal and suit comminuted fragments
- Keep screws within the epiphysis
Complications
- Arthrofibrosis is the most significant, reduced by early motion and timely surgery
- Residual laxity from ACL plastic deformation, with a minority needing later reconstruction
- Growth disturbance from physeal screws or tunnels
- Elevated malunion causing extension block from notch impingement
- Nonunion from interposed soft tissue
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.