
Definition
- A locally aggressive synovial tumour which affects both large joints & tendon sheaths
- Same entity as giant cell tumour of tendon sheath
Terminology
- Other names for this disorder have included
- synovial xanthoma
- synovial fibroendothelioma
- synovial endothelioma
- benign fibrous histiocytoma
- xanthomatous giant cell tumour
- myeloplaxoma
- chronic haemorrhagic villous synovitis
Epidemiology
- 1.8 per million
- No sex or racial predilection
- Most common in the 20s & 30s
Aetiology
- Essentially unknown
- Theories
- Hirohata
- localised disturbance in the metabolism of lipids
- Trauma.
- However, low incidence in patients with haemorrhagic disorders, & has not been consistently reproduced in experimental animals
- Inflammation
- Widest held theory since 1941 (Jaffe)
- Trigger for inflammation has not been identified
- Hirohata
Pathology
Gross
- Tan colour
- In the knee usually consists of multiple nodules, often with dramatic associated hyperplastic villous changes in the synovium, giving a straggly beard appearance
- Extensive haemosiderin deposition
Microscopic
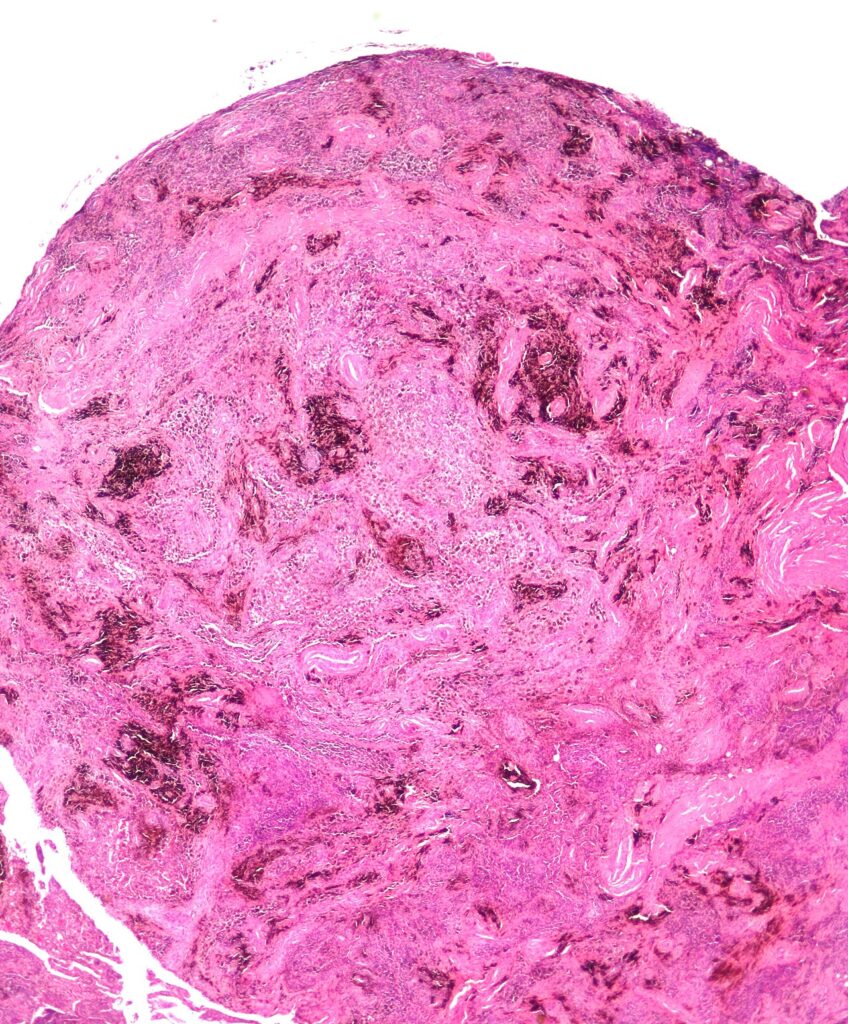
- Proliferating, collagen producing polyhedral cells
- Often scattered multinucleated giant cells
- Foam cells
- Haemosiderin
Clinical Presentation
- Much more frequently found as a solitary nodule & more rarely as a diffuse multinodular condition
- Most common sites are the knees & fingers
- Can also occur in the wrist, hip, ankle & toes
- Usually painless or only mildly painful. Onset is insidious
- Approximately 50% can recall an episode of trauma
Signs
- Local warmth
- Swelling
- Stiffness
- Palpable mass
- Point tenderness in 50%
Investigations
Aspiration
- produces a deep xanthochromic to brownish stained bloody fluid
X-ray
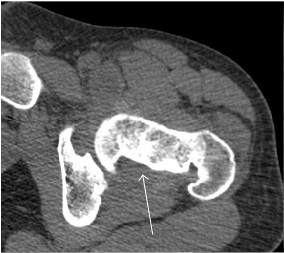
- Fingers
- usually only soft tissue swelling or there may be cortical erosion
- Knee
- major finding is soft tissue swelling which may be massive
- Erosion may cause a lytic intramedullary lesion. Erosion is rare in the knee because a substantial bulk of tumour can be accommodated, but is more common in the hip
- Lucencies on either side of a joint are very characteristic of PVNS
- Findings of extension outside the joint, calcification or cortical destruction suggest the diagnosis of synovial sarcoma
MRI
- low to intermediate signal intensity on T1 & T2 weighted images
Treatment
- Excision
- Options
- arthroscopic
- open using anterior & posterior approaches
- In the posterior approach, a lazy S incision is made, the gastrocnemius heads are released & the capsule opened using two T shaped incisions, one medial & one lateral
- menisci are detached both anteriorly & posteriorly & are later repaired
- Options
- Radiation synovectomy
- Radiocolloid yttrium-90 is injected into the knee
- Doesn’t appear to affect the knee cartilage
- External beam irradiation
- may be used. One dosage that has been used is 35Gy
- Tends to be used in recurrences
- Arthrodesis
- End stage destruction, particularly in the ankle, often requires arthrodesis
Prognosis
- Metastatic disease may develop
- MRI is effective in detecting recurrence postoperatively
- Recurrence is common in the diffuse form of the disease
- E.g. 33% in a series of 18 patients with PVNS of the knee
- In the localised form recurrence is uncommon
Reviewed by Professor Phong Tran, Head of Orthopaedic Surgery, Western Health. Last updated 10 October 2026.